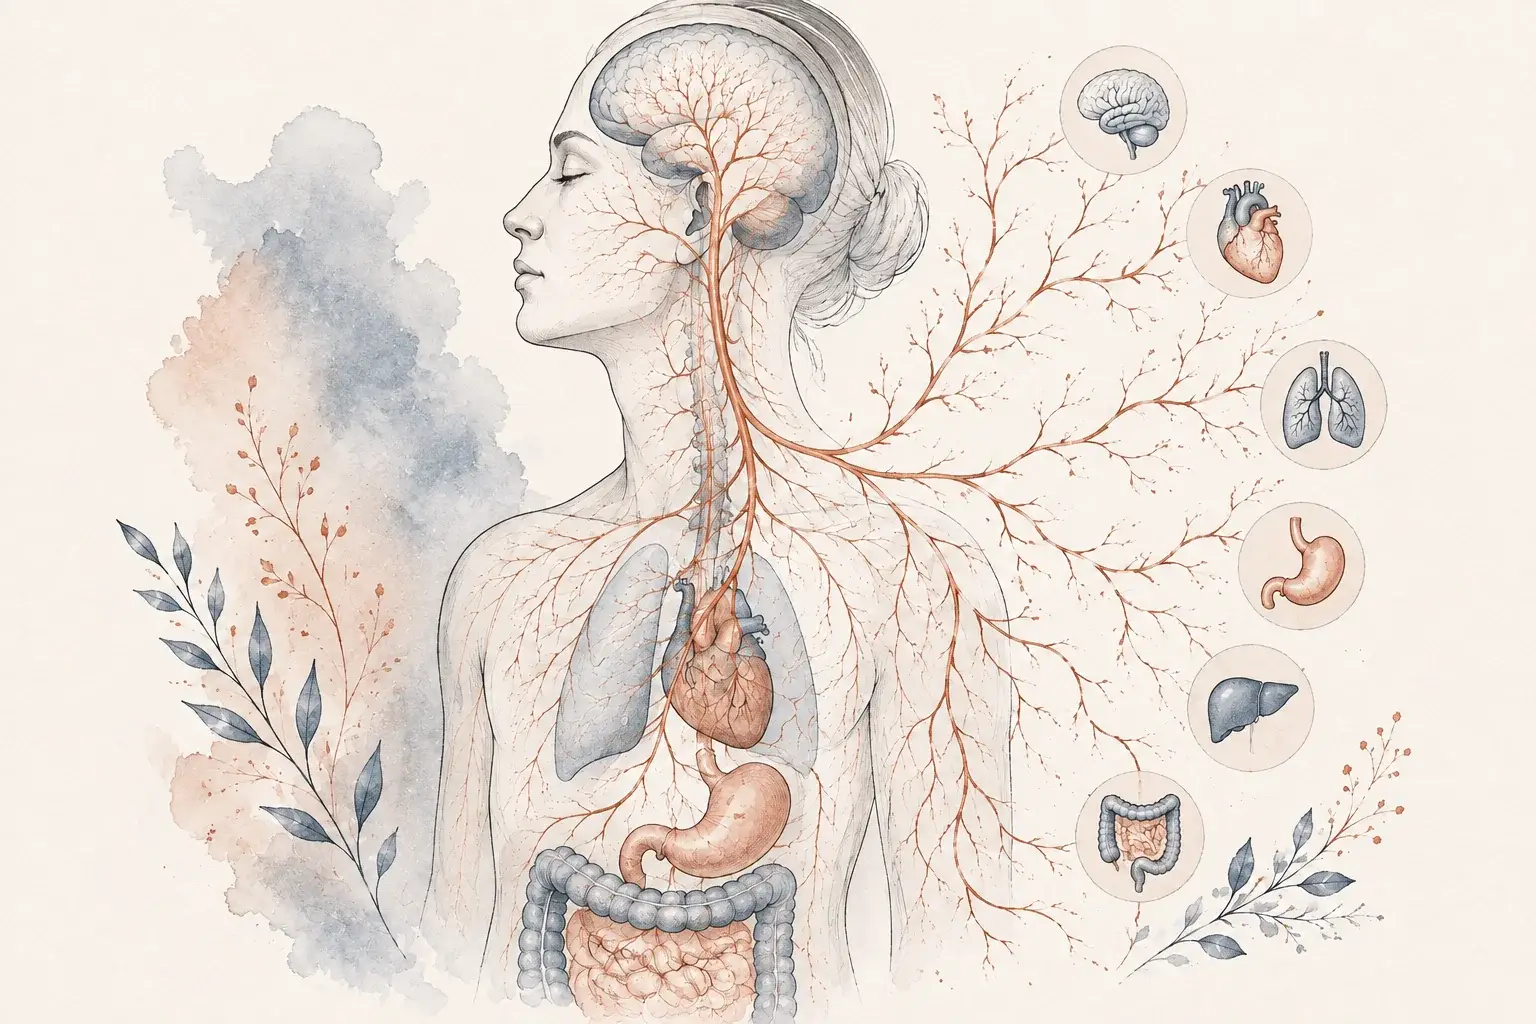
Most people who arrive with dysautonomia have already seen a cardiologist, a gastroenterologist, and a primary care doctor, and been told each system looks fine. That is what you would expect, because the problem is not in any one of those systems. It is in the nerves that run all of them.
What autonomic dysfunction means, and the terms you may be handed
The autonomic nervous system works without your attention: it speeds and slows the heart, tightens blood vessels when you stand, moves food through the gut, controls sweating, and empties the bladder. Autonomic dysfunction is any disorder in which that system stops regulating properly. Several other words describe the same territory, and it helps to know what each one is claiming.
- Dysautonomia is simply the medical word for autonomic dysfunction. It is an umbrella, not a diagnosis.
- Autonomic instability or autonomic dysregulation usually appears in a report when heart rate, blood pressure, or temperature are swinging more than they should. It describes what was observed, not why.
- Autonomic imbalance is a looser phrase, often used to mean that the sympathetic "accelerator" and parasympathetic "brake" are out of step. It is not a diagnosis either.
- Autonomic neuropathy means the autonomic nerves themselves are damaged, most often by diabetes, an autoimmune process, or small fiber neuropathy.
- Autonomic failure is the severe end, where the system can no longer hold blood pressure up on standing at all. It is seen in Parkinson's disease, multiple system atrophy, and pure autonomic failure.
If any of these phrases is on your chart, the next question is which specific disorder is behind it. That is what the evaluation below is for.
Autonomic dysfunction symptoms and signs
When the autonomic system stops regulating properly, the symptoms follow the systems it controls, which is why the list looks scattered until you see the pattern.
| System affected | What it looks like |
|---|---|
| Blood pressure | Lightheadedness, blurred vision, or fainting on standing |
| Heart rate | Palpitations or a racing pulse, worst in the first minutes upright |
| Digestion | Nausea, bloating, feeling full after a few bites, constipation or diarrhea |
| Sweating and temperature | Sweating too much or too little, and poor tolerance of heat |
| Bladder and sexual function | Urgency, incomplete emptying, sexual dysfunction |
| Exercise capacity | Exhaustion out of proportion to effort, worse when upright |
Visual guide
The body's automatic functions

- Circulation: Heart rate and blood pressure respond to changes in position.
- Digestion: Autonomic nerves help regulate the gut.
- Temperature: Sweating helps the body manage heat.
Types of autonomic nervous system disorders
- POTS (postural orthostatic tachycardia syndrome) is the form we see most often. The heart rate rises abnormally on standing while blood pressure stays roughly stable, producing a racing pulse, lightheadedness, brain fog, fatigue, headaches, and exercise intolerance. It mostly affects younger adults and is among the conditions most frequently dismissed as anxiety before anyone measures it. It is also one of the recognized patterns of long COVID; if a racing heart or exercise intolerance appeared in the months after an infection, it is worth measuring rather than waiting out.
- Orthostatic hypotension is the opposite pattern: blood pressure falls on standing. It is common with age, with certain medications, and in autonomic neuropathy and autonomic failure.
- Neurally mediated (vasovagal) syncope is fainting triggered by a sudden drop in heart rate and blood pressure, often after prolonged standing, pain, or heat.
- Autonomic neuropathy, from diabetes, small fiber neuropathy, or an autoimmune process, affects several systems at once, often with gut and sweating symptoms prominent.
- Autonomic failure syndromes, including multiple system atrophy and pure autonomic failure, are rarer, progressive, and are considered when orthostatic hypotension is severe or comes with movement or bladder symptoms.
Causes of autonomic dysfunction
| Cause | What it means for the workup |
|---|---|
| Diabetes | The most common cause of autonomic neuropathy, and the reason glucose control is checked first |
| Small fiber neuropathy | Damages autonomic fibers alongside sensory ones. Confirmed by skin biopsy |
| Autoimmune disease | Autoimmune autonomic neuropathy has specific antibody tests and specific treatment |
| Infection, including COVID-19 | A recognized trigger for POTS, often in a previously healthy person |
| Parkinson's disease and multiple system atrophy | Autonomic failure appears alongside movement symptoms |
| Medications, alcohol, and toxins | Reversible, and the first thing worth reviewing |
| Genetic conditions | Considered when there is a family history or an early onset |
In a fair number of patients, especially those with POTS, no single cause is found even after a thorough workup. That does not make the condition less real or less treatable.
How autonomic dysfunction is diagnosed
The history and the standing test
A detailed history across every system involved, a full neurological examination, and a medication review. Then the active standing test: you lie quietly for several minutes while heart rate and blood pressure are recorded, then stand for up to ten minutes with readings taken at intervals. A sustained rise of 30 beats per minute or more within ten minutes of standing, 40 or more in teenagers, without a fall in blood pressure, points to POTS. A drop of 20 mmHg systolic or 10 mmHg diastolic within three minutes points to orthostatic hypotension. This simple measurement is usually the most informative part of the visit.
Blood tests
Glucose, thyroid function, vitamin levels, and autoimmune antibody panels when the history fits, looking for causes that change the treatment.
A small fiber skin biopsy
A minor in-office procedure taking two or three tiny skin samples from the leg to count small nerve fibers under a microscope. It detects damage to autonomic as well as sensory fibers. More on the small fiber skin biopsy.
Formal autonomic testing
When the office measurements are equivocal, we order tilt table testing, sweat testing, and heart rate variability studies at a dedicated autonomic laboratory, then interpret the results with you. We do not run these tests in our office.
Imaging, only if the examination calls for it
Brain MRI when a structural cause is suspected. Most patients with dysautonomia have normal imaging and do not need a scan.
A word about smartwatches. Months of heart-rate data showing spikes on standing is genuinely useful history, and it is not a diagnosis. A watch cannot tell whether the rise was sustained, whether blood pressure fell at the same time, or whether anxiety, dehydration, a medication, or deconditioning explains it. Bring the data, and we measure it properly.
Visual guide
What changes when you stand
- Position: Heart rate and blood pressure may be checked lying and standing.
- History: Symptoms, medications, and possible causes add context.
- Further tests: More testing is selected when the findings call for it.
Treatment for autonomic dysfunction
Treatment aims at the cause where one is found, and at the symptoms in every case. Most patients need a combination rather than a single prescription.
- Fluids and salt to raise circulating volume, which is the foundation everything else is built on.
- Compression garments, waist-high rather than knee-high, which is the difference between working and not working.
- A graded exercise program, starting recumbent or seated, because deconditioning makes every form of dysautonomia worse and upright exercise is intolerable at first.
- Medication to steady heart rate or support blood pressure, chosen for your specific pattern, and separately for digestion when the gut is the main problem.
- Practical adjustments: raising the head of the bed, avoiding long periods of standing and hot environments, and smaller, more frequent meals.
- Treating the underlying cause, such as tighter diabetes control or immunotherapy for an autoimmune autonomic neuropathy.
Adjusting this takes several rounds. Medication effects on heart rate and blood pressure show up within days, so early follow-up is built into the plan rather than left to the next routine visit.
Who treats autonomic dysfunction, and when to see one
Neurologists diagnose and treat autonomic dysfunction, because the autonomic nerves are part of the nervous system and the evaluation is a neurological one. Cardiologists are often involved when fainting or heart rhythm is the main concern, and a primary care doctor usually co-manages the long-term plan. Frequent lightheadedness or fainting on standing, unexplained changes in heart rate, digestive problems with no gastrointestinal explanation, or trouble regulating temperature are all worth a neurological evaluation, particularly when they arrived together or when other specialists have found each system normal.
When it is an emergency
Fainting that causes an injury, fainting with chest pain or during exercise, new weakness or trouble speaking, or a resting heart rate that stays very high belongs in an emergency department, not an office visit.
Dysautonomia is diagnosed by assembling the whole picture, which is what a 60-minute visit is for. Dr. Achillefs Ntranos, MD is a board-certified neurologist whose practice focuses on autoimmune neurology and neuropathy, and he sees every patient himself. The standing measurements, the examination, and the biopsy happen in person, so you can request a visit in Beverly Hills or Los Angeles, and follow-ups work well by video.
Frequently asked questions
References
- Cleveland Clinic. Dysautonomia.
- National Institute of Neurological Disorders and Stroke. Dysautonomia.
- Sheldon RS, et al. 2015 Heart Rhythm Society expert consensus statement on the diagnosis and treatment of postural tachycardia syndrome, inappropriate sinus tachycardia, and vasovagal syncope. Heart Rhythm, 2015.
- Freeman R, et al. Consensus statement on the definition of orthostatic hypotension, neurally mediated syncope and the postural tachycardia syndrome. Clinical Autonomic Research, 2011.