
What is a seizure?
The brain works on electrical signals passed between billions of nerve cells in an orderly rhythm. A seizure is what happens when a group of those cells fires all at once, abnormally and out of step. Depending on where the burst starts and how far it spreads, the person may stare blankly for a few seconds, feel a strange sensation or a wave of fear, lose awareness, or stiffen and convulse. Most seizures stop on their own within a minute or two.
A seizure is a single event. Epilepsy is the brain's ongoing tendency to produce them without an obvious trigger, and one seizure does not establish it. Plenty of first seizures are provoked by an identifiable acute cause such as alcohol withdrawal, a medication, or low blood sugar, or set off by a trigger such as severe sleep loss, and never happen again once that cause is addressed. Whether a seizure was provoked is the first question a neurologist asks, because it changes everything that follows, including whether medication is discussed at all.
Visual guide
How seizures relate to brain activity
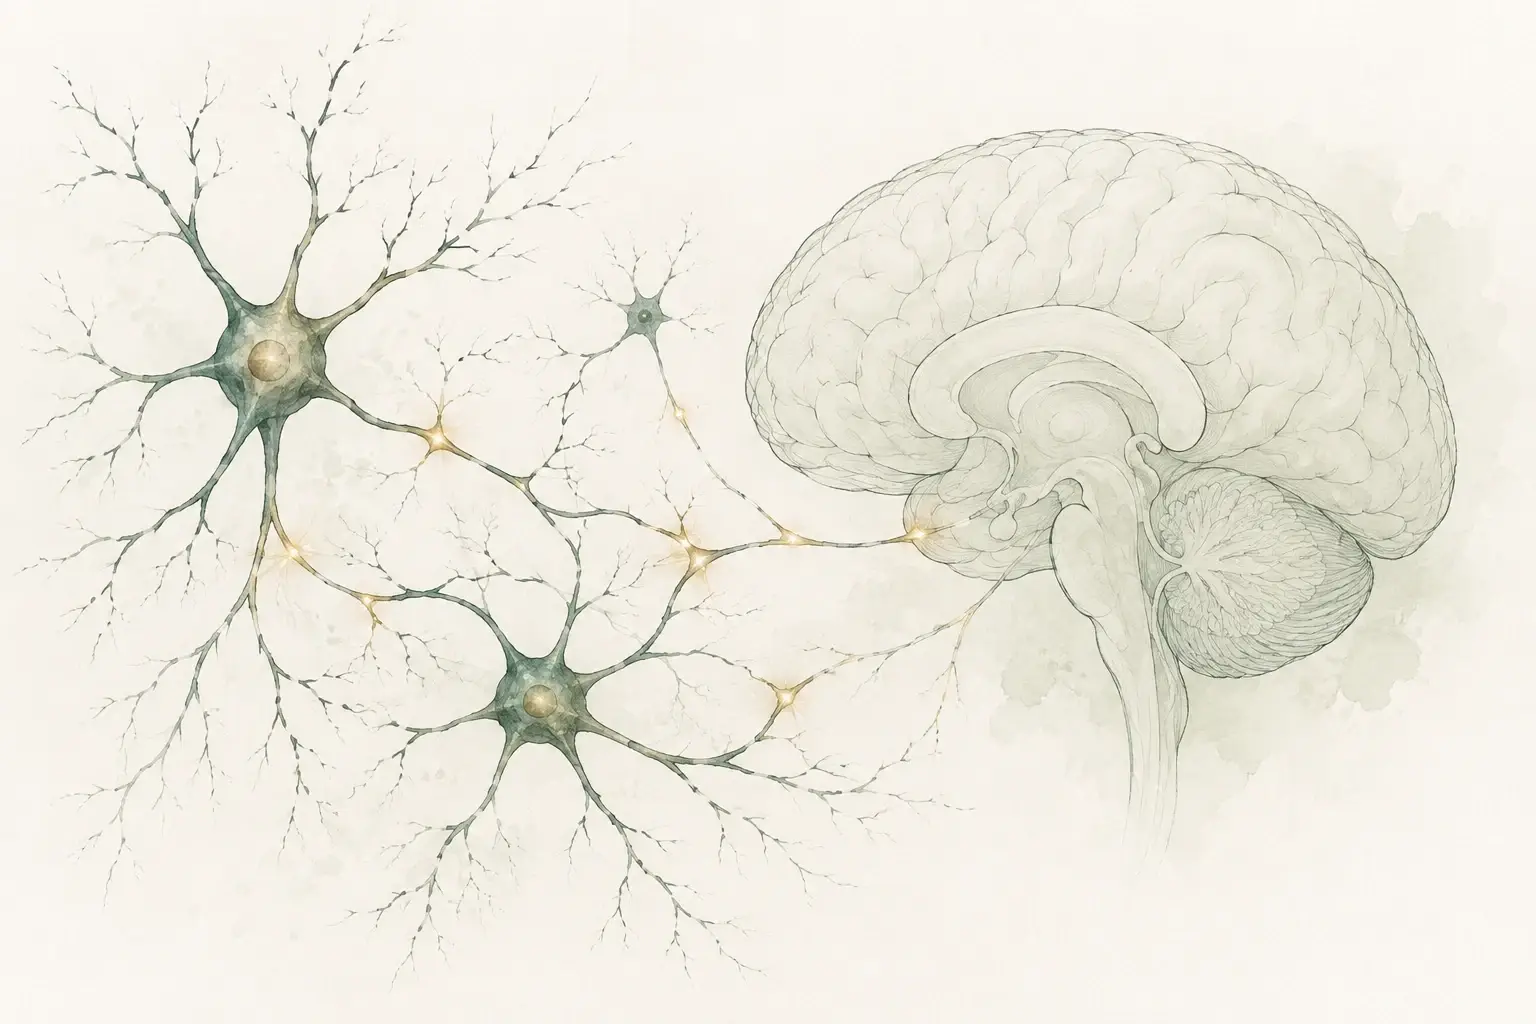
- Activity: Brain cells communicate through electrical signals.
- Seizure: Abnormal activity can briefly change awareness, movement, or sensation.
- Evaluation: History, EEG, imaging, and blood tests help guide care.
Types of seizures
Seizures are grouped by where in the brain they start. Focal seizures begin in one area. Generalized seizures involve both sides from the outset.
| Seizure type | What it looks like |
|---|---|
| Focal aware (once called simple partial) | Fully awake throughout. Tingling, flashing lights, an odd smell, or a wave of fear or déjà vu |
| Focal impaired awareness (once complex partial) | Staring, lip-smacking, fumbling, or wandering, with awareness clouded and confusion afterwards |
| Focal to bilateral tonic-clonic | Starts in one area, then spreads and becomes a full convulsion |
| Absence | Brief staring spells, usually in children, easily mistaken for daydreaming |
| Tonic-clonic (once grand mal) | Stiffening, then rhythmic jerking, with loss of consciousness |
| Atonic | A sudden loss of muscle tone that causes a fall |
| Myoclonic | Brief shock-like jerks, often shortly after waking |
Symptoms of a seizure, from the outside and the inside
Depending on the type: temporary confusion, staring, uncontrollable jerking of the arms and legs, loss of awareness, or purely internal symptoms such as fear, déjà vu, or a rising feeling in the stomach. Many people get a warning (an aura) beforehand, and most feel tired, headachy, or confused afterwards. Some notice a bitten tongue or that they lost bladder control.
Because almost nobody remembers their own seizure, a description from someone who watched it, or a phone video, is often the most useful thing a neurologist can be given.
What to do while someone is having a seizure
Stay with them and time it. Move hard objects away, put something soft under the head, and once the jerking stops, roll them onto their side so they can breathe easily. Do not hold them down and do not put anything in their mouth. Stay until they are fully awake and know where they are.
When a seizure is an emergency
Status epilepticus is a prolonged seizure, or seizures repeating with no recovery in between. Call 911 if a seizure lasts longer than five minutes, if normal behavior does not return afterwards, if a second follows soon after, if it happens in water or causes injury, if the person cannot be woken or has trouble breathing, if they are pregnant or have diabetes, or if it is a first seizure.
What causes seizures in adults
Causes vary with age. Genetic factors account for many epilepsies starting in childhood. In adults the usual candidates are head trauma including concussion, stroke (the most common cause in older adults), brain tumors, infections such as meningitis, brain malformations, and autoimmune encephalitis, an increasingly recognized cause of new adult seizures. Alcohol and drug withdrawal, some medications, and severe sleep loss provoke seizures in people who do not have epilepsy. In many people no cause is ever found, and that does not change how well the seizures respond to treatment.
The workup after a first seizure
The account of the event
What happened before, during, and after, from you and from anyone who saw it. This carries more diagnostic weight than any test.
Examination and blood tests
A neurological examination, plus blood work for provoking causes such as low sodium or glucose and to check organ function before any medication starts.
EEG
Records the brain's electrical activity and can show the pattern that identifies a seizure type. A normal EEG does not rule epilepsy out.
MRI
Looks for a structural cause. Preferably MRI rather than CT, since CT misses the small changes that matter here.
What the tests decide is the chance of a second seizure. After a single unprovoked seizure with a normal EEG and MRI, most people never have another. When the EEG shows epileptic activity or the MRI shows a lesion, the chance of recurrence is high enough that neurologists diagnose epilepsy after one seizure and usually recommend treatment. That is the decision the workup exists to inform.
Not every spell that looks like a seizure is one. Fainting, migraine aura, sleep disorders, and psychogenic non-epileptic events are common mimics, and separating them sometimes needs prolonged EEG monitoring.
Visual guide
The workup after a first seizure
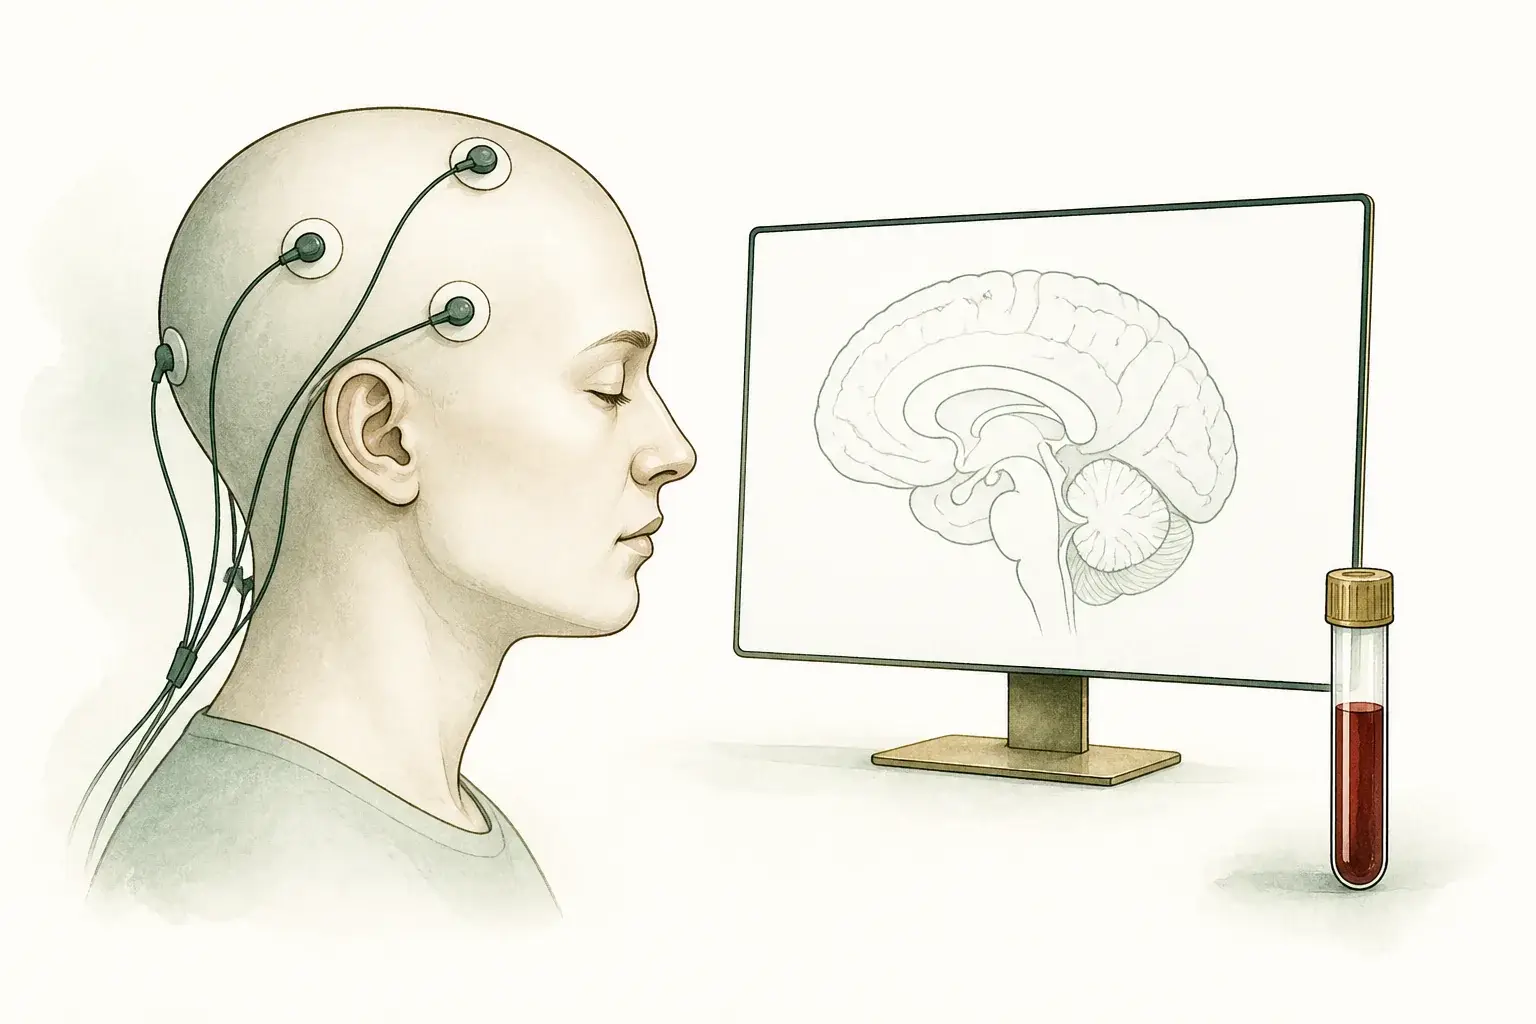
- EEG: Brain-wave recording looks for relevant electrical patterns.
- MRI: Imaging looks for structural explanations.
- Blood tests: Selected tests check for contributing medical problems.
Epilepsy treatment
The goal is no seizures and no side effects, and most people get close to both.
Medication is the main treatment, and most people become seizure-free on the first or second anti-seizure drug. The choice depends on the seizure type, your age, your other medications, plans for pregnancy, and which side effects you most want to avoid. We adjust on how you are doing, not only on a blood level.
Surgery is for seizures that continue despite two well-chosen medications. Removing or disconnecting the area where seizures start can be highly effective. That evaluation happens at a comprehensive epilepsy center, and we refer when it fits.
Dietary therapy, the ketogenic diet and its less restrictive variants, reduces seizures particularly in children with hard-to-control epilepsy. It is a medical treatment and needs a dietitian.
Neurostimulation devices (vagus nerve, responsive, and deep brain stimulation) help people who are not surgical candidates or whose seizures persist afterwards, and are also arranged through an epilepsy center.
Alongside any of these: take the medication exactly as prescribed and tell us before stopping it, protect your sleep (deprivation is the most common trigger we see), limit alcohol, and keep a seizure diary.
Driving after a seizure in California, and when to see a neurologist
See a neurologist after a first seizure, if seizures are becoming more frequent or are not controlled, if you have new side effects, if you are considering pregnancy, or if the DMV has asked for an evaluation.
Driving is the question most adults ask first. In California, Health and Safety Code section 103900 requires physicians to report any patient aged 14 or older diagnosed with a disorder characterized by lapses of consciousness to the local health officer, who passes it to the DMV. The DMV then decides on the license. It generally requires a period of seizure freedom, the length of which depends on the circumstances of the seizure and the medical evaluation. Some situations are considered differently, including a first isolated seizure, seizures that happen only during sleep, and a seizure caused by a change in medication directed by your physician. We do not set the rules, but we complete DMV driver evaluations and can tell you at the visit what is likely to apply to you. Pilots need an FAA neurological evaluation, which we also prepare.
A visit here is 60 minutes with Dr. Ntranos, a board-certified neurologist. We take the account, examine you, and order the EEG, MRI, and blood tests through your insurance, then review what the results mean for medication, driving, and work. You can request a visit in Beverly Hills or Los Angeles, and once the diagnosis is settled most follow-up works well by video anywhere in California. We do not perform epilepsy surgery or prolonged EEG monitoring ourselves; when either is needed we refer to a comprehensive epilepsy center.
Frequently asked questions
References
- Fisher RS, et al. ILAE official report: a practical clinical definition of epilepsy. Epilepsia, 2014.
- Centers for Disease Control and Prevention. Types of Seizures.
- National Institute of Neurological Disorders and Stroke. Epilepsy and Seizures.
- Chen Z, et al. Treatment outcomes in patients with newly diagnosed epilepsy treated with established and new antiepileptic drugs. JAMA Neurology, 2018.
- California DMV. Lapse of Consciousness Disorders.
- California Health and Safety Code section 103900. Reporting of disorders characterized by lapses of consciousness.