Genetic testing is easy to order and hard to order well. Laboratories sequence hundreds of genes at once, and a test chosen without a clear clinical question returns variants nobody can interpret. The useful sequence runs the other way: examine the patient, define the pattern, let the pattern choose the test.
Which neurological disorders can genetic testing diagnose?
A result can confirm what the examination suggested, end a search that has run through years of inconclusive tests, tell relatives whether they are at risk, and in a growing number of conditions point to a treatment. It is not available for everything, which is the part patients are most often misled about.
| Condition family | Genetic diagnosis available | What a result changes |
|---|---|---|
| Hereditary neuropathy: Charcot-Marie-Tooth, transthyretin amyloidosis | Yes | The amyloid form is treatable |
| Muscular dystrophies and inherited myopathies | Yes | Confirms the diagnosis and what to monitor |
| Ataxias, spastic paraplegias, Huntington's disease | Yes, by repeat-expansion assay | Explains progressive imbalance and informs relatives |
| Familial ALS and motor neuron disease | In a minority | Some genes now have targeted therapies |
| Epilepsy from childhood or with a family pattern | Often | The gene can direct the medication choice |
| Early-onset dementia, CADASIL | Sometimes | In late-onset memory loss, cognitive testing first |
| Multiple sclerosis, common migraine | No | Diagnosis rests on MRI and examination |
Repeat-expansion disorders deserve a note. Huntington's disease, many ataxias, myotonic dystrophy, and the C9orf72 form of ALS need a separate assay, because standard panels miss them. That is a common reason a previous negative test was incomplete.
The types of genetic test
In increasing breadth: a single-gene test when the picture points to one condition; a panel of genes grouped by presentation, which is the right test for most patients; a repeat-expansion assay where one is needed; and exome or genome sequencing when panels have found nothing. Broader is not better. The wider the net, the more uncertain variants it returns, and the more it costs to interpret them. Testing parents or siblings alongside you often makes an exome result readable.
Visual guide
Choosing a genetic test
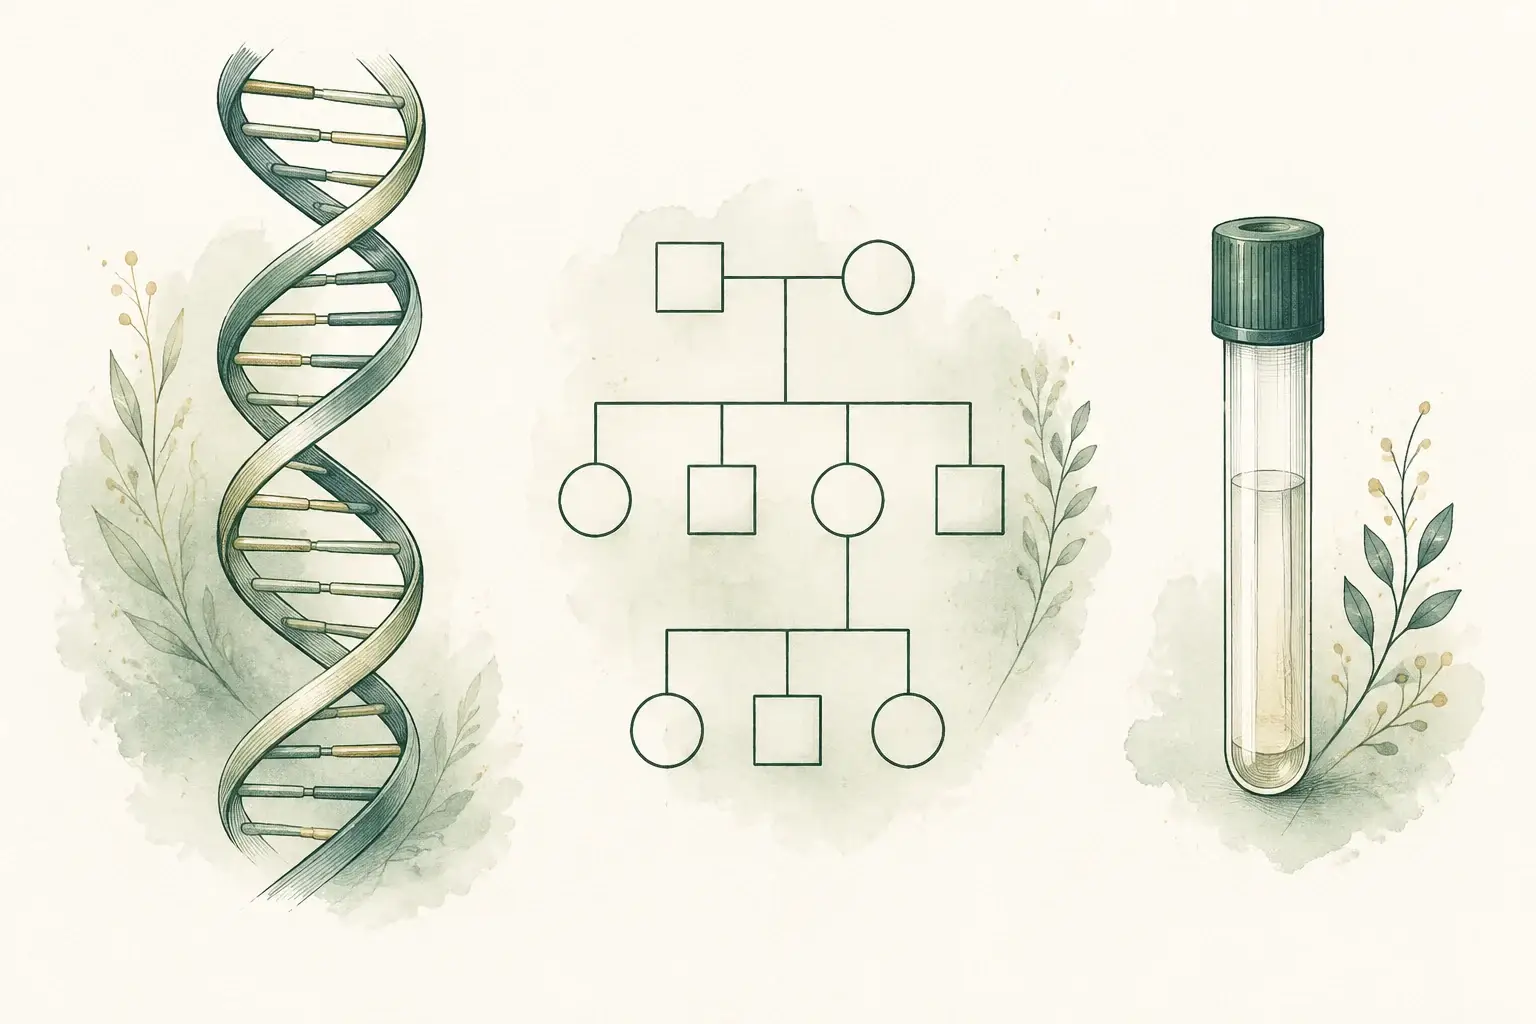
- Define the pattern: review symptoms and a three-generation family history.
- Choose the assay: a panel, single-gene test or other assay answers a specific question.
- Discuss first: understand possible results and costs before giving a sample.
What a result actually means
A positive result in a gene that matches your presentation confirms the diagnosis, usually ends further invasive testing, sometimes opens a treatment or a trial, and gives relatives the option of an accurate test for the same variant.
A negative result is less final than it sounds. It lowers the likelihood of the conditions tested and says nothing about the ones that were not, and panels are revised every year. We treat it as one piece of the workup, not the end.
Predictive testing, meaning a test in someone with no symptoms, is accurate when a specific familial variant is known. For adult-onset conditions without a treatment, such as Huntington's disease, the standard of care is to work through that decision with a certified genetic counselor first. We arrange the referral. Some people choose to test, many choose not to, and both are reasonable.
How testing works here
The consultation
Sixty minutes with Dr. Achillefs Ntranos, MD, in person or by video: history, a three-generation family tree, examination, and prior testing. When the honest answer is that testing will not help, we say so.
Choosing the test
The pattern from the examination and family tree picks one of the test types above. If you have already had a negative test, we check what it actually covered, because a panel that skipped the repeat-expansion assay has not excluded the conditions that need it.
Consent, cost, and the sample
What the test can and cannot find, the chance of an uncertain result, and how the laboratory bills. Nothing is ordered until you have those answers. Then a blood draw or a saliva kit, run at a CLIA-certified laboratory.
Results and plan
Dr. Ntranos reads the report against your examination and explains it plainly: positive, negative, or uncertain, and what that means for you and your family. Treatment, monitoring, referrals, or family testing, written down.
Variants of uncertain significance
A variant of uncertain significance is a change the laboratory cannot yet call harmful or harmless, usually because it is too rare for anyone to have seen it often enough to know. The larger the panel, the more of them you get. A VUS is not a diagnosis, and professional guidelines say it should not be used to make medical decisions.
Our job is to decide whether it fits your presentation, whether testing relatives would clarify it (a variant present in an unaffected parent is usually benign), and whether anything should change meanwhile, which is usually nothing. Laboratories reclassify variants as evidence accumulates, most often toward benign, and we revisit open variants at follow-up.
Visual guide
Making sense of a genetic result

- Positive: a relevant finding can confirm a matching clinical diagnosis.
- Negative: the result only addresses what that test could detect.
- Uncertain: a variant of uncertain significance is not a diagnosis.
Before you decide
A result can land heavily whichever way it goes: relief at having a name, or grief, guilt about children, worry about relatives. We talk about that before testing, not only after, and involve a certified genetic counselor whenever the decision or the result calls for it. We do not provide mental health treatment, and will help you find it.
Privacy is worth settling before the sample is drawn. The FAQ sets out what the law does and does not protect.
Questions worth sitting with:
- What would I do differently with a positive result, and with a negative one?
- Do I want to know about a condition that cannot yet be treated?
- How will I tell my relatives, and do they want to know?
- Am I planning a family, and would the result change those plans?
Cost and booking
Our visits are flat-fee and not billed to insurance. You receive a superbill, and most PPO plans reimburse 50–80%, depending on out-of-network benefits and deductible. HSA and FSA cards are accepted. See billing.
The laboratory bills your insurance for the test itself, and we handle the prior authorization. Coverage varies by plan, and most laboratories also offer a self-pay price and financial assistance. We tell you the options before the sample is drawn.
If you have symptoms that might be inherited, a relative with a genetic diagnosis, or a report you would like explained, book a consultation or call (310) 774-7025. Having an existing result read in context is a common reason for a second opinion.
Frequently asked questions
References
- Richards S, et al. Standards and guidelines for the interpretation of sequence variants: a joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genetics in Medicine, 2015.
- National Human Genome Research Institute. Variant of uncertain significance (VUS).
- MedlinePlus. What is genetic testing?
- National Human Genome Research Institute. Genetic discrimination and the Genetic Information Nondiscrimination Act.