
A migraine is not just a bad headache. It is a neurological condition that can take out a day or more, and it is one of the most treatable conditions we see. An attack is not a single event: it moves through phases, and each one is a chance to act earlier than the last.
What a migraine is
A migraine is more than a headache. Where tension-type headache causes steady pressure, migraine is a neurological disorder in which the brain's processing of light, sound, smell, and pain changes during an attack. No blood test or scan confirms it. The diagnosis comes from the pattern, which with a normal neurological examination rarely needs imaging. If you do have a scan, migraine is one of the common reasons for small white spots on a brain MRI.
Vestibular migraine, where vertigo is the main event, and aura without headache, sometimes called silent migraine, are variants of the same condition and are covered below.
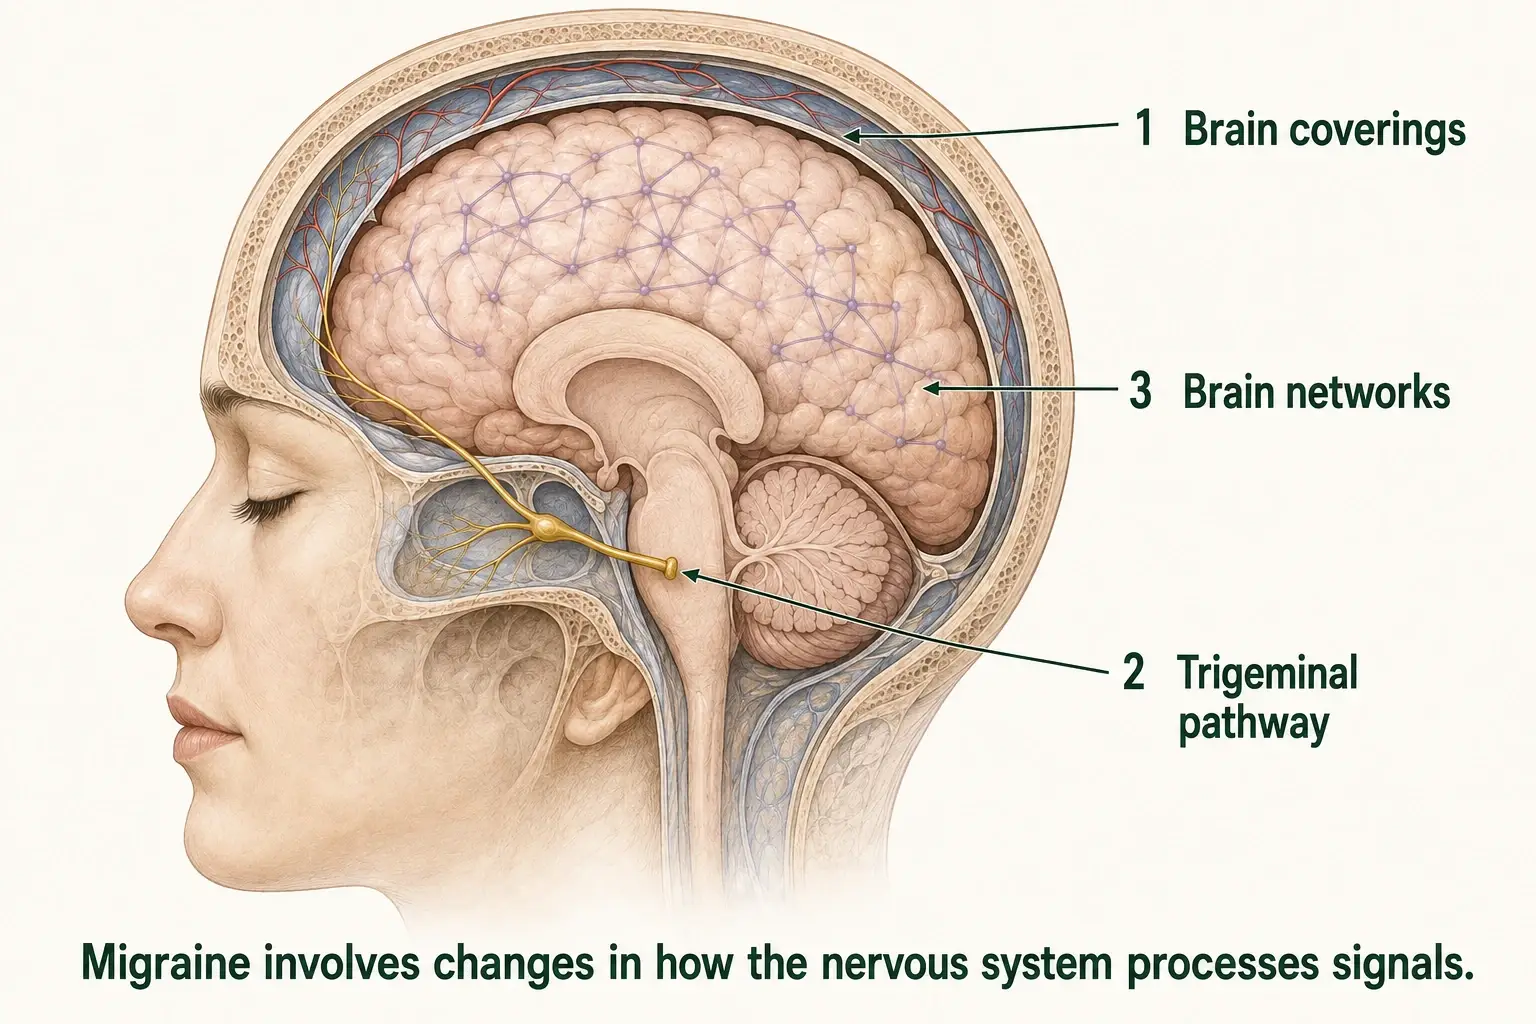
A closer look at migraine pain
Brain coverings
The tissues around the brain contain pain-sensitive nerve endings.
Trigeminal pathway
This nerve pathway carries pain signals from structures in the head toward the brainstem.
Brain networks
Connected brain regions process pain and other sensations during an attack.
The four phases of a migraine
Not everyone has all four, and the same person can experience them differently between attacks.
| Stage | Phase | When | What you notice |
|---|---|---|---|
| 1 | Prodrome | Hours to a day or two before the pain | Irritability or low mood, repeated yawning, fatigue, food cravings, neck stiffness, frequent urination, trouble concentrating |
| 2 | Aura, in a minority of people | 5 to 60 minutes per symptom, usually just before the headache | Flashing lights, zigzag lines, blind spots, tingling in the face or hand, difficulty speaking |
| 3 | Headache | A few hours to three days | Throbbing, often one-sided, with nausea, dizziness, and sensitivity to light, sound, and smell |
| 4 | Postdrome | Hours to a day or two after the pain stops | The migraine hangover: drained, foggy, slowed, scalp tenderness |
Most people skip stage 2: only a minority of people with migraine have aura, so for most the prodrome runs straight into the headache.
Prodrome vs aura at a glance
| When | How long | What you notice | Who gets it | What to do | |
|---|---|---|---|---|---|
| Prodrome | Hours to a day or two before the pain | Usually a few hours, sometimes a day, occasionally two | Mood change, yawning, tiredness, cravings, a stiff neck, poor focus | Most people with migraine, though not before every attack | Start your plan early: eat, drink water, rest, and take any treatment it sets for this stage |
| Aura | Usually just before the headache, and sometimes with no headache after it | 5 to 60 minutes per symptom | Flashing lights, zigzag lines, a blind spot, tingling that spreads, trouble finding words | A minority of people with migraine | Follow your plan's timing: a triptan waits for the pain to start. Symptoms that are sudden, new to you or last over an hour mean call 911 |
Prodrome: the first stage, and how long it lasts
Prodrome is the phase worth knowing well, because it is the widest window. Treating inside it can stop the attack before the pain starts.
The symptoms are easy to dismiss because none of them is a headache. Mood shifts are the most common, usually toward irritability or a low, occasionally toward unusual energy. Prodrome usually lasts hours, sometimes up to a day, and occasionally two, and it does not happen before every attack.
| Symptom | What people notice | Why it matters |
|---|---|---|
| Yawning | Yawning again and again without feeling sleepy | Few people connect it with migraine; if it comes before your attacks, it is a cue to act |
| Hunger and cravings | Hunger out of proportion, or a craving for something specific, such as chocolate | The craving is an early sign of the attack, not its cause (more below) |
| Irritability or anger | A short fuse, snapping at people, feeling on edge | Mood change is the most common prodrome sign, and it lifts as the attack passes |
| Low mood | Feeling flat, sad or tearful for no clear reason | It passes with the attack; low mood that stays between attacks needs care of its own |
| Anxiety | Restlessness, worry, a sense that something is off | It also passes with the attack; anxiety between attacks is worth raising at a visit |
| Fatigue | Heavy tiredness, wanting to lie down | Easy to blame on a bad night when it can be the attack starting |
| Neck stiffness | A tight, aching neck or shoulders | Often blamed on posture or a pillow when it can be the first stage of a migraine |
| Frequent urination | Needing the bathroom more often than usual | Easy to miss; worth a line in your diary |
| Light and sound sensitivity | Lights seem too bright and ordinary noise grates | Dimming the lights and cutting the noise early lowers the load on the brain |
| Trouble concentrating | Losing your train of thought, rereading the same line | A cue to pause and start the steps in your plan |
One trap: prodrome symptoms are easy to mistake for causes. If you crave chocolate and then get a migraine, it is natural to blame the chocolate, when the craving was the first sign of an attack already underway. A migraine diary, tracking food, sleep, mood, and symptoms in the day or two before each attack, settles it within weeks.
Treating during prodrome is now an active area: a phase 3 trial tested ubrogepant taken during the prodrome, and it roughly doubled the chance of avoiding a moderate or severe headache. That use is off-label, since the drug is approved for treating attacks, but for people whose prodrome reliably predicts an attack it is a plan a neurologist can write, within the medication-overuse limit described below.
Prodrome without a headache
Sometimes a prodrome fizzles out without a headache, especially once attacks are well controlled. That is usually good news. Eating, drinking water, resting or taking the treatment your plan sets for this stage may have stopped the attack before the pain, or the attack simply never built. Log it in your diary like any other attack, because it shows your early signs are real and worth acting on.
New numbness, weakness or trouble speaking is never prodrome. If symptoms like these come on suddenly or are new to you, do not wait to see whether a headache follows: call 911. When they come with your usual attacks and settle within the hour, they are more likely aura, covered next; describe them to your neurologist all the same.
How to stop a migraine at the aura stage
Aura is shorter and more specific than prodrome, so the window is narrow: visual changes, tingling that spreads from the hand to the face, or trouble finding words, building over five minutes or more and lasting up to an hour per symptom. When symptoms come one after another the whole aura can run longer, and weakness can last far longer.
What to do in the aura should be decided before it happens. When we prescribe an acute medication, the plan says when to use it. Triptans have been tested during the aura itself and do not head off the headache, so a triptan is timed to the start of the pain, not the aura. Some other medications can be taken sooner. Your plan says which applies to you. If you do not have a plan that answers this question, that is the reason for a visit.
Beyond medication, a dark quiet room, water, and something small to eat all help, because sensory load, dehydration, and low blood sugar deepen an attack.
When aura symptoms are an emergency
Sudden visual loss, numbness, weakness, or trouble speaking that is new to you, comes on abruptly rather than building over minutes, or lasts more than an hour can be a stroke rather than a migraine. So can a thunderclap headache, meaning a severe headache that peaks within a minute. Call 911. Our article on when to worry about a headache covers the rest.
Silent migraine: aura without the headache, and how long it lasts
A silent migraine is an aura with no headache after it. The zigzag lines, the blind spot or the spreading tingling come and go, and the pain you braced for never arrives. It happens more often after 50, and it can be unsettling precisely because there is no headache to explain it.
Each aura symptom lasts 5 to 60 minutes. When one follows another, vision first and then tingling, the whole episode runs longer, but each visual or sensory symptom usually settles within the hour. Symptoms that last hours or days are not typical aura and need a prompt evaluation rather than waiting it out. And a first-ever aura after age 40, with or without a headache, needs a transient ischemic attack, a brief interruption of blood flow in the brain, excluded before it is put down to migraine, because the same symptoms can come from one.
Postdrome: the last stage, and how long it lasts
Postdrome is the migraine hangover: exhaustion, fog, slowed thinking, a tender scalp, mood swings, and sometimes a dull residual ache that flares when you bend over. It usually lasts hours to a day, occasionally two. Rest, fluids, and avoiding bright light and strong smells help.

The phases of a migraine
- Before pain: Prodrome can begin before the headache; aura occurs in some people.
- Headache: Pain and associated symptoms form the main attack.
- Afterward: Postdrome may leave lingering fatigue or a hangover feeling.
When the migraine hangover lasts days or weeks
A true postdrome is measured in hours, occasionally two days. A hangover that seems to last days or weeks is usually something else, and it is worth finding out which, because each is treated differently from a single long attack:
- Attacks running together. Short gaps between attacks can feel like one long hangover. This is the pattern of chronic migraine, headache on 15 or more days a month, and it calls for prevention rather than more rescue doses.
- Medication overuse. Pain relievers or triptans taken on more than two or three days a week can themselves keep the headaches going, a pattern called medication-overuse headache. The way out is a planned change with your neurologist, usually alongside a preventive, not more of the same.
- Poor sleep. Attacks break up sleep, and short or broken sleep makes the next attack more likely, so tiredness and fog can carry on between attacks. Snoring or waking unrefreshed is worth mentioning at your visit.
- Aura that has not cleared. Tingling, numbness, weakness or visual change that persists after an attack belongs to the aura, not the postdrome. If it outlasts the attack it needs an evaluation, promptly if it is new to you.
A neurologist starts with the calendar: how many headache days you have in a month, on how many of them you take something, and how you sleep. Then a neurological examination, a review of every medication and supplement you take, and imaging only when the story or the examination points to it. That separates a long hangover from a run of attacks, and the answer decides the treatment.
What triggers a migraine
With the caveat that some apparent triggers are really prodrome symptoms:
- Hormonal changes, especially around menstruation
- Skipped meals, too little sleep, or too much sleep
- Stress, and the letdown after stress
- Alcohol, especially red wine, and inconsistent caffeine
- Bright light, loud sound, strong smells, weather changes, sudden exertion
Locally, our guide to Southern California migraine triggers covers Santa Ana winds and wildfire smoke.
Non-medication strategies
Routine is the foundation. The migraine brain dislikes change more than any particular food. Same bedtime and wake time including weekends, no skipped meals, enough water, and regular moderate exercise rather than sudden effort.
Mind-body techniques. Biofeedback has the strongest evidence; progressive muscle relaxation and mindfulness-based stress reduction have also cut attack frequency.
Supplements studied specifically for prevention:
| Supplement | What the evidence shows | Worth knowing |
|---|---|---|
| Magnesium | Probably effective, Level B, in the 2012 AAN and AHS guideline, since retired | Often where we start |
| Riboflavin (vitamin B2) | Probably effective, Level B, in the same 2012 guideline | Slow; judge after a few months |
| CoQ10 | Possibly effective, the weakest evidence level | The positive trial was in adults |
| Butterbur | Recommendation withdrawn | Trials showed benefit, but the AAN and AHS withdrew their recommendation in 2015 after reports of serious liver injury, including with products labeled free of pyrrolizidine alkaloids. We do not recommend it |
The evidence ranges from low to moderate quality, product quality varies, and none of these is a substitute for a preventive when one is needed. Tell us what you plan to take, particularly alongside other medications or with liver or kidney disease.

Tracking what affects your migraines
- Diary: Record attacks and possible triggers to look for patterns.
- Routine: Regular sleep, meals, and hydration can help.
- Care: Frequent or disabling attacks deserve an individualized treatment plan.
Medications for migraine
Treatment has two halves: stopping an attack, and preventing the next one.
| What it is for | Options | |
|---|---|---|
| Acute | Stopping an attack that has started | Ibuprofen or naproxen, triptans, gepants such as ubrogepant or rimegepant, lasmiditan, ergotamines, plus an anti-nausea medication |
| Preventive | Reducing how often attacks happen | Certain antidepressants, beta blockers, anti-seizure medications, CGRP antibody injections such as erenumab, fremanezumab or galcanezumab, a daily gepant such as atogepant, calcium channel blockers for migraine with aura |
Two rules matter more than the choice of drug. Acute medication taken on more than two or three days a week causes medication-overuse headache, so that is the point to move to prevention rather than take more. And preventives need several weeks at a steady dose before their effect is clear, so we adjust at follow-up rather than switch early.
Botulinum toxin injections are approved for chronic migraine, meaning headache on 15 or more days a month for more than three months, at least eight of them with migraine features. We do not perform them at our offices, so when chronic migraine calls for them we say so and refer you.
When to see a neurologist
See one if migraines interfere with work or sleep, stop responding to over-the-counter medication, or you are reaching for a pain reliever most days. The same goes for a new or changed pattern, attacks with weakness, numbness, or trouble speaking, and unexplained vertigo. A sudden, intense headache unlike your usual attacks needs emergency care, not an appointment.
Dr. Achillefs Ntranos, MD sees migraine patients through our headache neurology service. A first visit is 60 minutes and most of it is the history, because that is what makes the diagnosis. You leave with a written plan for acute treatment and prevention, including what to do in the prodrome and the aura. One attack can take out a day; with that plan, the next one does not start with guesswork. Follow-ups are usually every one to three months and last 30 minutes. Pilots who need an FAA neurological evaluation should say so in their request. Request a visit in person in Beverly Hills or Los Angeles, or by video anywhere in California; no referral needed, and the office confirms within 1 business day.
Frequently asked questions
References
- American Migraine Foundation. The timeline of a migraine attack.
- The Migraine Trust. Prodrome: spotting the first signs of a migraine attack.
- Cleveland Clinic. Migraine hangover (postdrome).
- Ailani J, Burch RC, Robbins MS. The American Headache Society consensus statement: update on integrating new migraine treatments into clinical practice. Headache, 2021.
- Dodick DW, et al. Ubrogepant for the treatment of migraine attacks during the prodrome (PRODROME): a phase 3, randomised, double-blind, placebo-controlled, crossover trial. Lancet, 2023.
- National Center for Complementary and Integrative Health. Butterbur.
- Holland S, et al. Evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention in adults. Neurology, 2012.
- Slater SK, et al. A randomized, double-blinded, placebo-controlled, crossover, add-on study of coenzyme Q10 in the prevention of pediatric and adolescent migraine. Cephalalgia, 2011.
- Bates D, et al. Subcutaneous sumatriptan during the migraine aura. Neurology, 1994.
- Olesen J, et al. No effect of eletriptan administration during the aura phase of migraine. European Journal of Neurology, 2004.
- International Classification of Headache Disorders, 3rd edition. Migraine with aura.
- International Classification of Headache Disorders, 3rd edition. Chronic migraine.
- DailyMed. Ubrelvy (ubrogepant) prescribing information. National Library of Medicine.
- American Migraine Foundation. Understanding the new anti-CGRP treatments.