
Pain that shoots from the neck into an arm, or from the low back down a leg, is one of the most common reasons people see a neurologist. Most settle on their own. The job is to spot the ones that will not, and to confirm the nerve under pressure is a root at the spine rather than a nerve further down the limb.
What is a pinched nerve, and what is radiculopathy?
A pinched nerve is any nerve squeezed hard enough by the tissue around it, bone, disc, muscle, or tendon, that it stops working properly. Carpal tunnel syndrome is a pinched nerve at the wrist.
Radiculopathy is the case where the pressure falls on a nerve root, where the nerve leaves the spinal canal. Each root supplies a strip of skin and a set of muscles, so the symptoms land in a narrow, predictable band rather than the whole limb. A pinched nerve in the neck, cervical radiculopathy, reaches the shoulder, arm, and hand. A pinched nerve in the low back, lumbar radiculopathy, reaches the leg and foot, and sciatica is its most familiar form. A trapped nerve in the shoulder is usually one of the upper neck roots rather than a nerve in the shoulder itself.
Visual guide
Where nerve pressure can occur
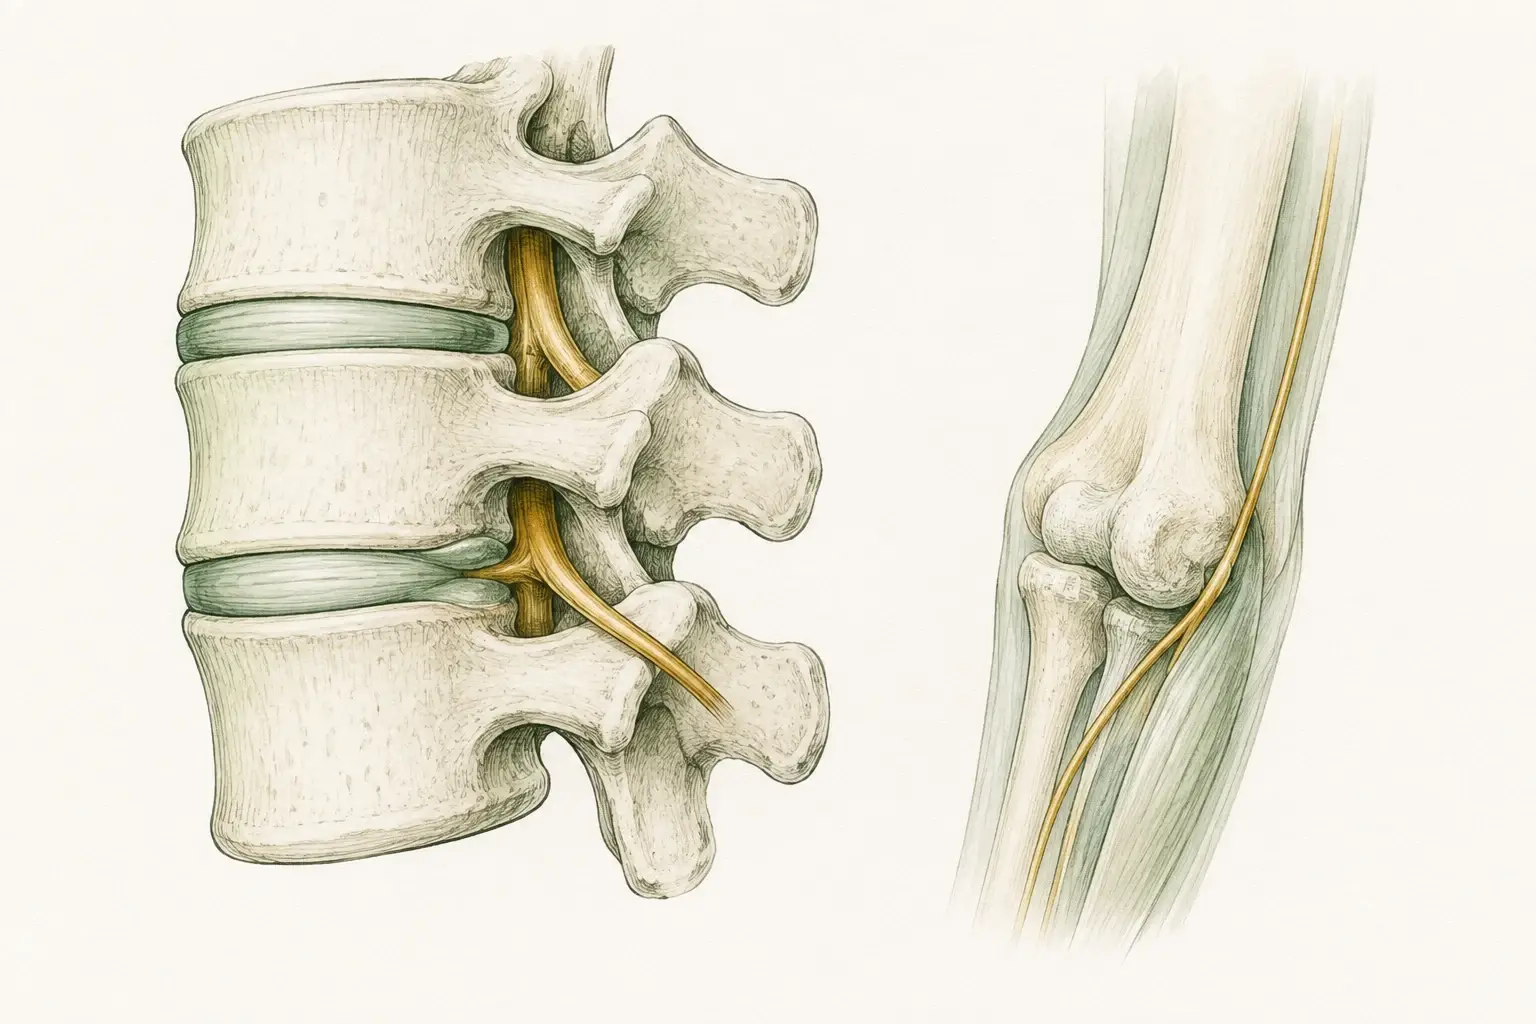
- Spine: Pressure on a nerve root is called radiculopathy.
- Pathway: Pain, tingling, or weakness can follow the affected nerve.
- Examination: The symptom pattern helps locate the source.
Pinched nerve symptoms: where each root sends pain
Symptoms are a sharp, burning, or electric pain along a line, with tingling and numbness on the same path, worse with coughing, sneezing, and certain positions. This map is what the examination checks against.
| Root | Where the pain and numbness go | Typical weakness |
|---|---|---|
| C5 | Neck to shoulder and outer upper arm | Lifting the arm out to the side |
| C6 | Down the arm to the thumb and index finger | Bending the elbow, cocking the wrist back |
| C7 | Down the back of the arm to the middle finger | Straightening the elbow |
| C8 | Inner forearm to the ring and little fingers | Grip, spreading the fingers |
| L4 | Front of the thigh across to the inner shin | Straightening the knee |
| L5 | Buttock, outer thigh and shin, top of the foot, big toe | Lifting the foot, foot drop |
| S1 | Back of the thigh and calf to the sole and little toe | Pushing off, standing on tiptoe |
The map is a guide, not a rule. Root territories overlap, they vary from person to person, and a root under pressure often produces only part of its pattern: pain without numbness, numbness without weakness, or symptoms that stop at the shoulder. Two overlaps cause most of the confusion. A C6 root and carpal tunnel syndrome both numb the thumb and index finger; a C8 root and an ulnar nerve at the elbow both numb the little finger. Neck pain, change with neck position, and a dropped reflex point to the root. That is the main reason hand numbness reaches a neurologist.
Anatomy at a glanceThe neck and arm
Why neck problems can reach the arm
A nerve root connects the spinal cord with nerves that travel into the arm.
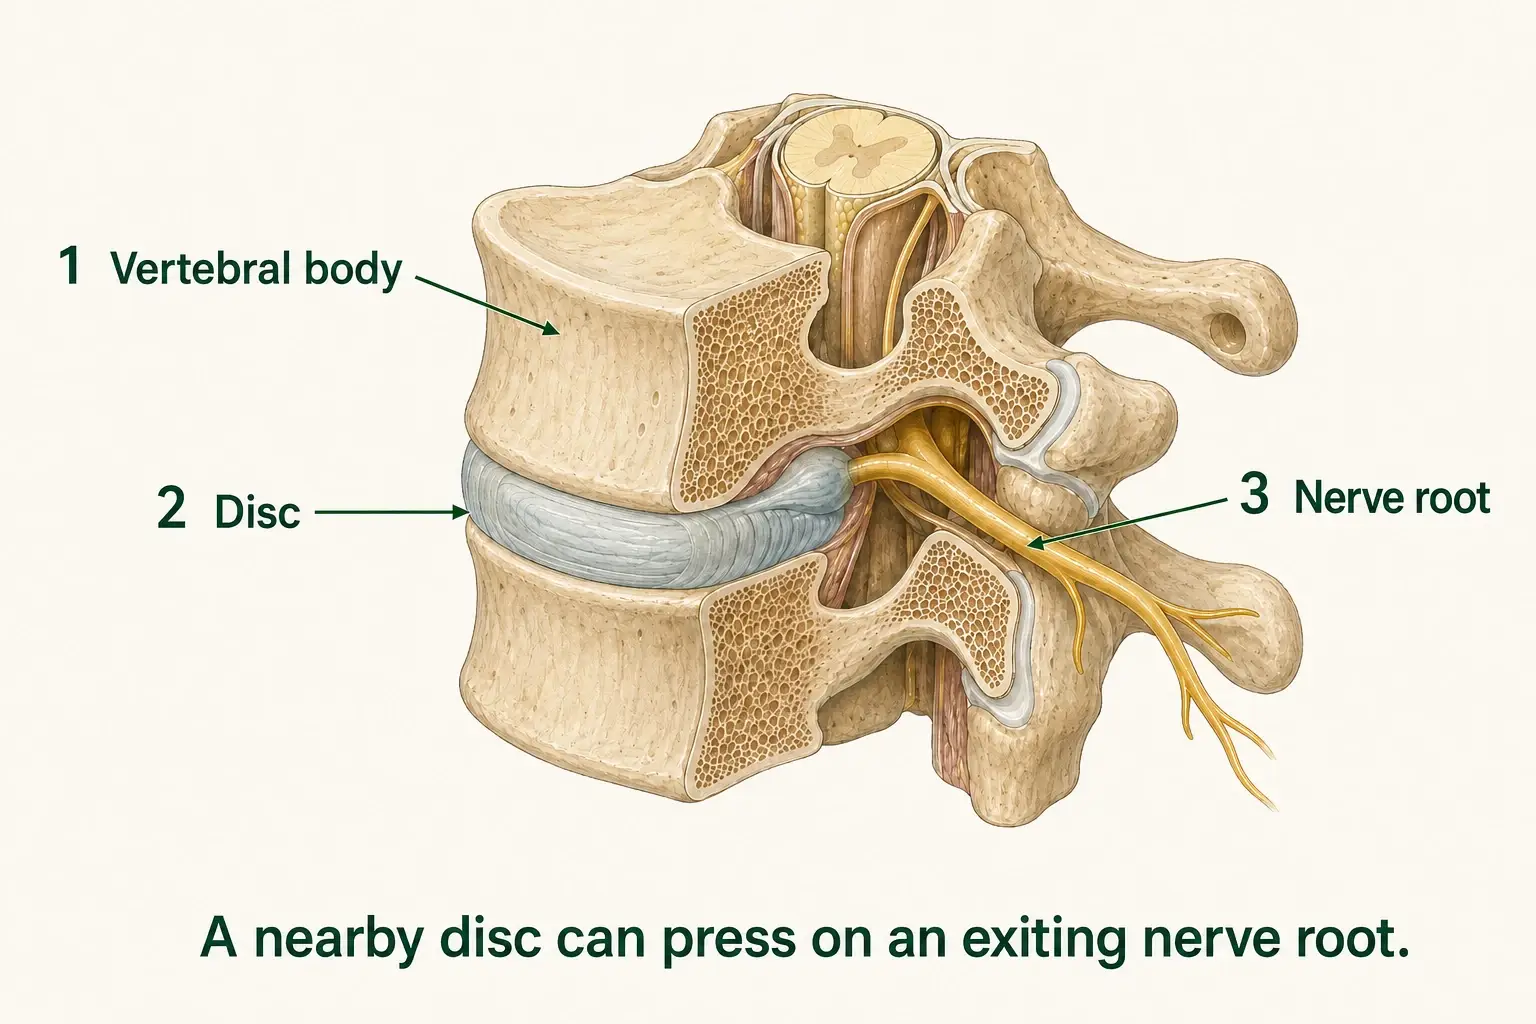
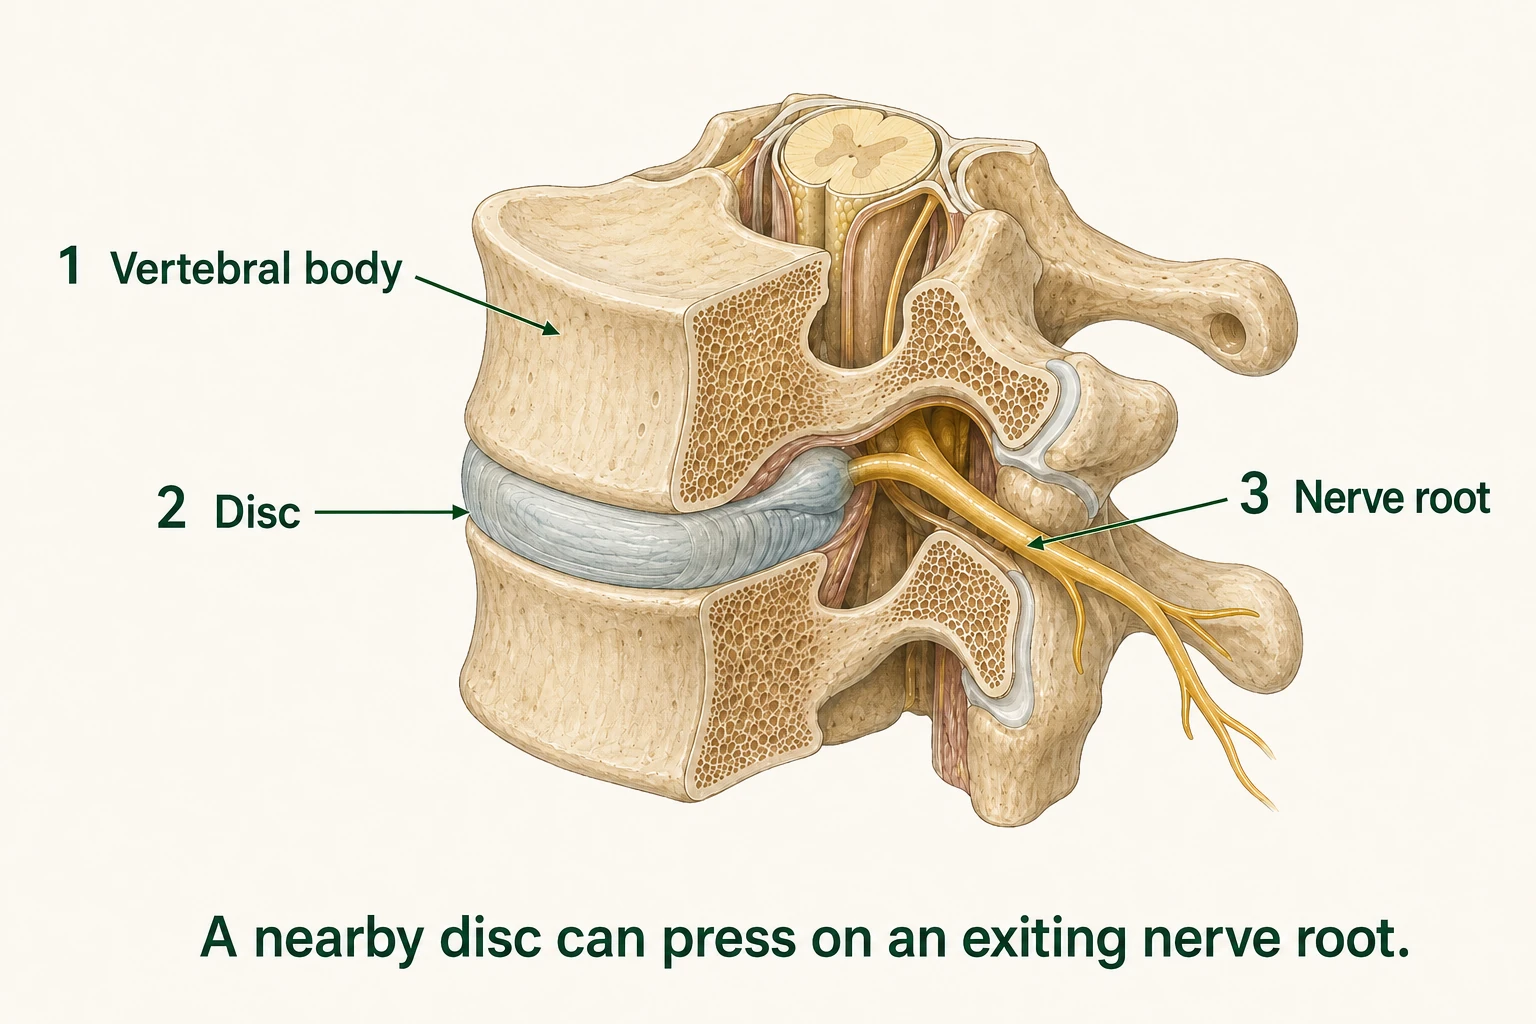
Vertebral body
The front, weight-bearing part of a spinal bone. Nerve roots leave through openings farther back, between neighboring bones.
Disc
A cushion between vertebrae. A herniated disc can press toward a nearby nerve root.
Nerve root
Irritation or pressure can cause pain, tingling, numbness, or weakness farther along the nerve.
Symptoms may be felt along the nerve, away from the neck.
Simplified neck anatomy showing one possible cause of nerve-root compression. Not every disc change causes symptoms.
Burning, twitching, and a pinched nerve without pain
Nerves that feel on fire. Burning is what an irritated sensory nerve produces when it fires on its own. Burning that follows one root's path, and changes with neck or back position, belongs to the root. Burning in both feet or both hands, spreading slowly and worse at night, is the pattern of peripheral neuropathy, which is a different workup.
Muscle twitching and spasms. A compressed root can make the muscles it supplies twitch, cramp, or spasm, and the neck or back muscles around a painful root often go into protective spasm. Twitching on its own, without pain, numbness, or weakness in that root's territory, is usually not a pinched nerve; our muscle twitching page covers the other causes. Twitching with weakness or wasting is a reason for nerve testing.
No pain at all. Yes, a pinched nerve can present with numbness or weakness alone. Painless weakness is, if anything, the more important version, because it can progress quietly.
What causes it
- Herniated disc, the most common cause in younger adults, bulging onto the root
- Spinal stenosis, narrowing of the canal or the openings the roots pass through, more common with age
- Bone spurs from arthritis of the spine
- Injury, including whiplash and falls
- Load and posture, from prolonged neck flexion and repetitive lifting to weight gain and pregnancy
Red flags: same-day emergency care
Loss of bladder or bowel control, numbness in the groin or inner thighs, rapidly worsening leg weakness, or new difficulty walking can mean the spinal cord or the cauda equina is compressed. Go to an emergency department; delay risks permanent nerve damage.
How it is diagnosed
The neurological examination does most of the work: where sensation is reduced, which muscles are weak, which reflex has dropped, and which movements reproduce the pain. Together those identify the root before any scan.
- MRI for weakness, a red flag, or symptoms not improving after several weeks.
- EMG and nerve conduction studies confirm the problem is at the root rather than further down the limb, and help when an MRI shows changes at several levels.
The common pitfall is treating the scan instead of the person. Painless disc bulges are very common on MRI, so the imaging has to match the examination before anyone acts on it.
Treatment
Most radiculopathies improve with conservative treatment alone, which is where nearly everyone starts.
- Relative rest and activity change, without prolonged bed rest, which slows recovery.
- Physical therapy and a home exercise program, the treatment with the most durable effect. Stretches for a pinched nerve in the neck are best set up by a therapist, because the right ones depend on which root is involved and the wrong ones aggravate it.
- Medication: anti-inflammatories for the first weeks, sometimes a short course of oral steroid, and a nerve-pain medication such as gabapentin when the pain is burning or electric.
- An epidural steroid injection to the compressed root, which can shorten a severe episode.
- Spinal manipulation helps some people, but not when there is real weakness or any sign of spinal cord involvement.
Surgery is considered for progressive weakness, disabling pain after weeks of conservative treatment, or pressure on the spinal cord. Microdiscectomy removes the fragment pressing on the root; laminectomy or foraminotomy makes space where stenosis is the problem. We do not perform surgery, and refer to a spine surgeon when it is the right step.
Visual guide
Reducing pressure and supporting recovery
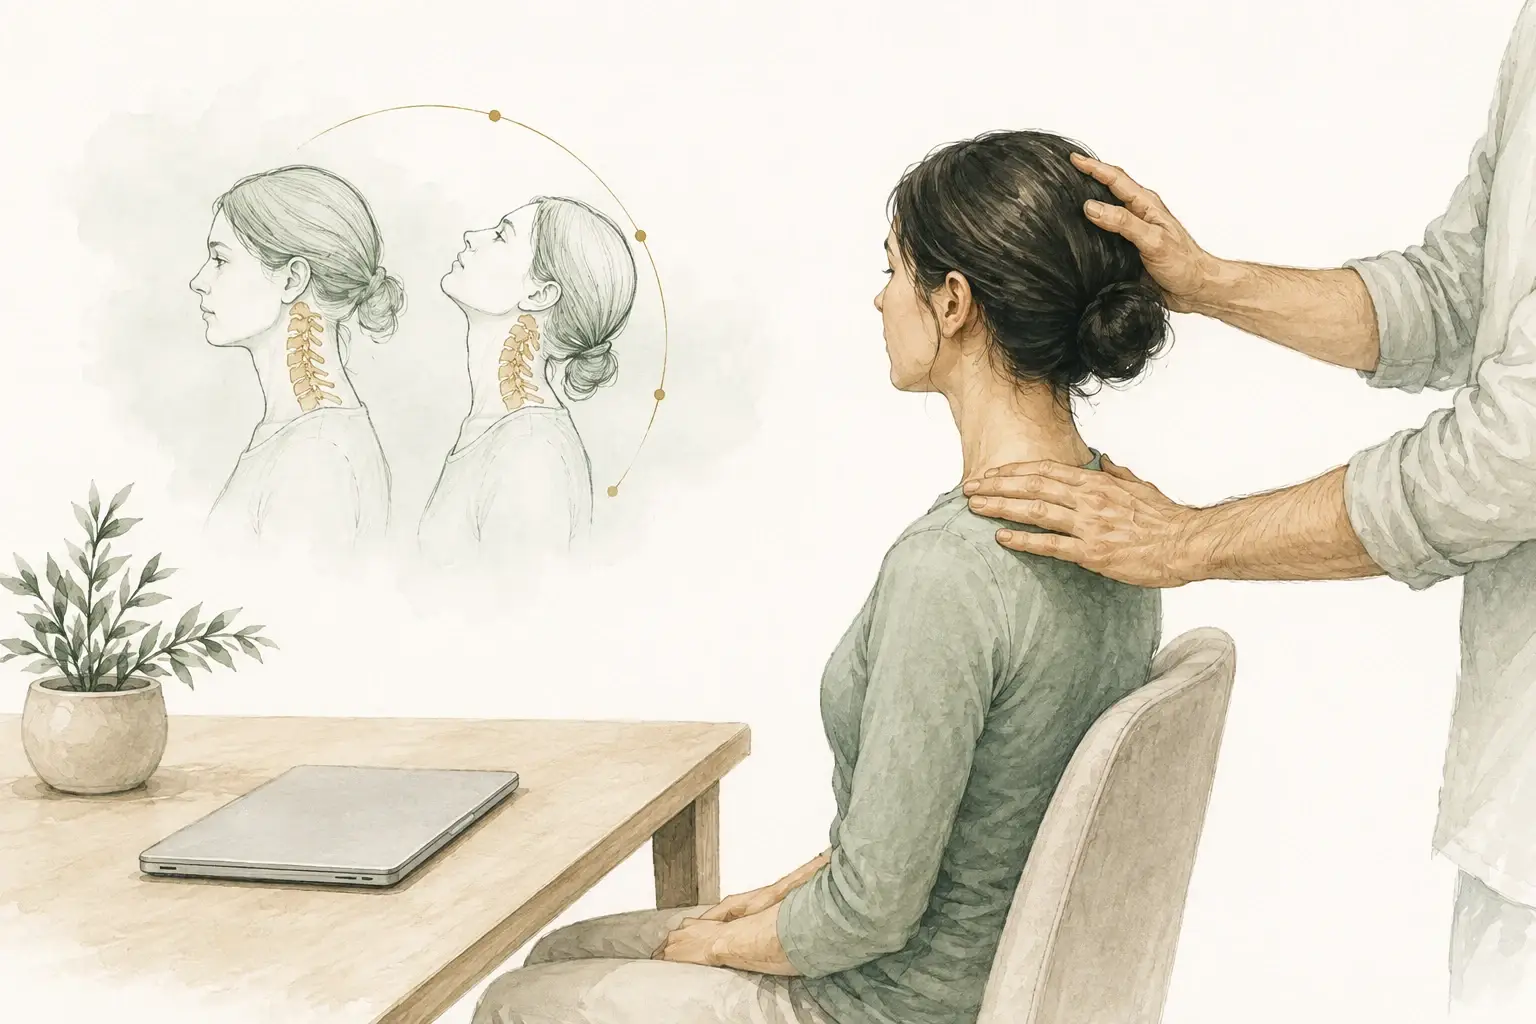
- Activity: Changes can reduce movements or positions that aggravate symptoms.
- Rehabilitation: Physical therapy is part of care for many people.
- Review: Persistent or worsening weakness can change the treatment plan.
When to see a neurologist
See one for weakness, for pain or numbness lasting more than a few weeks, or when nobody has been able to say whether the problem is the neck, the limb, or the nerves in general.
Dr. Achillefs Ntranos, MD sees these patients in Beverly Hills and Los Angeles. A first visit is 60 minutes, most of it the examination that identifies the root and rules out peripheral neuropathy. MRI is ordered when warranted, and the office handles prior authorization. We do not perform EMG or nerve conduction studies here; when they are needed we arrange them nearby and review the results with you. A video visit works well for follow-up, though a new radiculopathy is best examined in person. You can request a visit in Beverly Hills or Los Angeles, or by video anywhere in California.