Carpal tunnel syndrome is the most common nerve compression we see, and the most common cause of numbness and tingling in the hand. The diagnosis is usually clear, the testing is simple, and most people get better without surgery.
What is carpal tunnel syndrome?
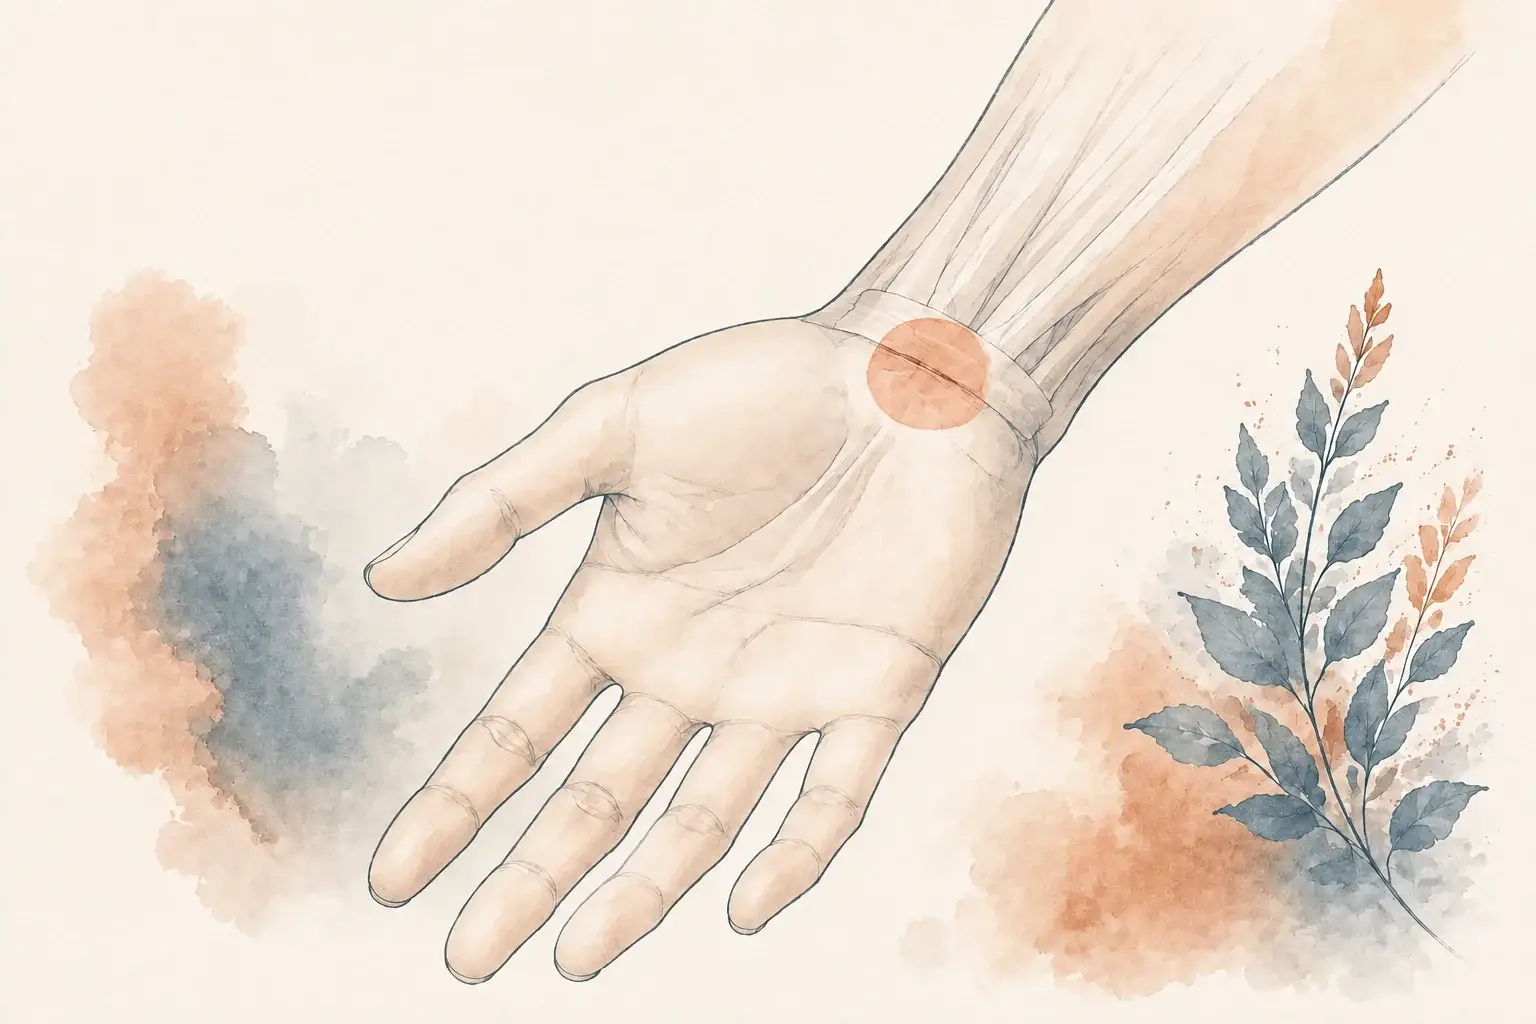
The carpal tunnel is a narrow passage on the palm side of the wrist, bounded by bone and a thick ligament. It carries the finger tendons and the median nerve. Anything that swells the tendons or narrows the space presses on the nerve. Median nerve compression at the wrist is the textbook name for the result.
That nerve supplies feeling to the thumb, index, middle, and half of the ring finger, and powers the muscles at the base of the thumb. The symptoms fall exactly there, which is what makes the pattern so recognizable. The little finger is spared, because a different nerve supplies it.

The median nerve at the wrist
- Location: The median nerve passes through a narrow space at the wrist.
- Sensation: Tingling often affects the thumb, index, and middle fingers.
- Pattern: Symptoms are commonly worse at night.
Carpal tunnel symptoms
- Numbness, tingling, or burning in the thumb, index, middle, and half the ring finger
- Symptoms that wake you at night, or appear while driving or holding a phone
- Aching in the hand, wrist, or forearm, sometimes reaching the shoulder
- A feeling that the fingers are swollen when they are not
- Later: weakness gripping or pinching, and dropping things
Forearm pain is common, because an irritated nerve sends pain up its own length as well as down it. Forearm pain on its own, with no numbness in the fingers, is usually not carpal tunnel syndrome and more often a tendon or neck problem.
How it progresses
Early carpal tunnel syndrome is intermittent: numbness at night or after a long drive that shaking the hand clears. Next it appears during the day with ordinary tasks. Later the numbness becomes constant, grip weakens, and the muscle at the base of the thumb thins. Nerve conduction studies grade the compression as mild, moderate, or severe, which is what most people mean by the stages of carpal tunnel.
Signs the nerve is being damaged
Numbness that is constant rather than coming and going, visible thinning of the muscle at the base of the thumb, or dropping objects means the nerve is already losing fibers. That moves things from "try a splint" to "get tested now", because recovery is less complete once muscle is lost.
Causes and risk factors
| Factor | Why it matters |
|---|---|
| Repetitive gripping, wrist flexing, or vibration | Swells the tendons that share the tunnel |
| Diabetes, thyroid disease, rheumatoid arthritis, kidney disease | Make the nerve more vulnerable and the tunnel tighter |
| Pregnancy | Fluid retention raises pressure in the tunnel; usually resolves after delivery |
| Prior wrist fracture or arthritis | Narrows the tunnel structurally |
| A naturally narrow tunnel | Partly inherited, which is why it often runs in families |
New carpal tunnel syndrome in both hands is worth a second look. It is sometimes the first sign of thyroid disease, diabetes, or an inflammatory arthritis.

Inside the carpal tunnel
Ligament roof
A strong band of tissue forms the roof. Wrist bones form the floor and sides of the tunnel.
Median nerve
Pressure on this nerve can cause tingling, numbness, or weakness in the hand.
Flexor tendons
Nine tendons pass through the tunnel alongside the nerve. They help bend the fingers and thumb.
How carpal tunnel is diagnosed
Most of the diagnosis is the history and the examination: which fingers, when, and whether the thumb muscles are weak or wasted. Two bedside tests help. Tapping over the nerve at the wrist may send tingling into the fingers, and holding the wrists bent for a minute may reproduce the symptoms.
Nerve conduction studies measure how well the median nerve carries a signal across the wrist and grade the compression as mild, moderate, or severe. They are worth doing when the diagnosis is uncertain, when surgery is being considered, or when more than one problem may be present.
Is it your wrist, your elbow or your neck?
The other half of the job is making sure the wrist is actually the source. The nearest look-alike is the ulnar nerve at the elbow, sometimes called cubital tunnel syndrome. A pinched nerve root in the neck can numb the same fingers as the wrist, which is why the neck is examined as carefully as the hand.
| If the numbness is | The likely source is | Clue |
|---|---|---|
| Thumb, index, middle fingers; worse at night | Carpal tunnel (median nerve at the wrist) | Little finger spared; shaking the hand helps |
| The little and ring fingers | Ulnar nerve at the elbow (cubital tunnel) | Worse when the elbow is bent or leaned on |
| Thumb and index finger, or the middle finger, with neck pain | A pinched nerve in the neck, the C6 or C7 root | Changes with neck position; an arm reflex may be reduced |
| Both hands and both feet | Peripheral neuropathy | Started in the feet; the whole hand rather than selected fingers |
Two can be true at once, such as carpal tunnel syndrome on top of a diabetic neuropathy, or a wrist and a neck problem in the same arm, which is why the examination follows the nerve all the way from the neck to the fingers. Our hand numbness page maps every other pattern finger by finger.
Nerve conduction results: mild, moderate or severe
If you have had a nerve conduction study, the report usually grades the compression. The grade describes how much the nerve has been affected, and together with how much the symptoms disrupt your life, it guides what comes next.
| Grade | What the study shows | What usually comes next |
|---|---|---|
| Mild | The signal slows as it crosses the wrist, mainly in the sensory fibers that carry feeling | A night splint and changes to the activities that provoke it |
| Moderate | Slowing in the sensory fibers and in the motor fibers that run the thumb muscles | The same steps, often adding a corticosteroid injection, and a discussion of release surgery if symptoms persist |
| Severe | A very weak or absent signal, sometimes with EMG signs that the thumb muscle has lost part of its nerve supply | Referral to a hand surgeon to discuss release, because the nerve is already losing fibers |
The grade is always read alongside your symptoms and the examination: constant numbness with a mild study, or a severe study with few symptoms, changes the plan. Recovery is more complete when the pressure is relieved before the thumb muscle has thinned.
Treatment
Almost everyone starts conservatively, and for most people that is enough.
- A night splint keeps the wrist straight while you sleep, which is when pressure in the tunnel peaks. Worn nightly over several weeks, it relieves many mild and moderate cases on its own.
- Activity changes to the specific tasks and positions that provoke it, including keyboard and phone habits.
- Hand therapy, including nerve-gliding and tendon-gliding exercises taught by a therapist. Exercises on their own rarely settle carpal tunnel syndrome. Combined with a splint they do better than a splint alone, and they are the part of treatment people can keep doing.
- A corticosteroid injection into the tunnel reduces swelling around the nerve and can give months of relief. A good response also helps confirm the diagnosis.
If those fail, or if testing shows severe compression or the thumb muscle is thinning, carpal tunnel release surgery is the definitive fix. The surgeon divides the ligament forming the roof of the tunnel. It is a short outpatient procedure that relieves symptoms in most people, and we refer to a hand surgeon when it is the right step.

Supporting the wrist
- Splint: A night splint can keep the wrist in a neutral position.
- Activity: Adjustments may reduce pressure that aggravates symptoms.
- Severity: Persistent numbness or weakness can change treatment choices.
Neurologist or hand surgeon: who to see for carpal tunnel
People often ask whether carpal tunnel is a neurologist's problem or an orthopedic one. Both treat it. A neurologist's part is localization: confirming the wrist is the problem, and not the neck or the nerves generally, before anyone injects or operates. A hand surgeon's part is the release when it is needed. See a neurologist if the numbness has lasted more than a few weeks, wakes you at night, comes with weakness, or does not stay in the fingers the median nerve supplies.
Worried that numb fingers mean surgery? Almost everyone starts with simpler steps, once a neurologist has confirmed the wrist is the problem. Dr. Achillefs Ntranos, MD usually sees carpal tunnel patients in person, because the diagnosis rests on a hands-on examination: a 60-minute first visit, mostly history and examination. We do not perform nerve conduction studies in our office; when they are needed we arrange them nearby and review the results with you. Follow-ups are usually every one to three months and last 30 minutes, and messages between visits are answered within 1 business day. Request a visit in Beverly Hills or Los Angeles, or by video anywhere in California; no referral needed, and the office confirms within 1 business day.
Frequently asked questions
References
- National Institute of Neurological Disorders and Stroke. Carpal tunnel syndrome.
- American Academy of Orthopaedic Surgeons, OrthoInfo. Carpal tunnel syndrome.
- American Academy of Orthopaedic Surgeons, OrthoInfo. Carpal tunnel syndrome therapeutic exercise program.
- Mayo Clinic. Carpal tunnel exercises: can they relieve symptoms?
- Cleveland Clinic. Carpal tunnel syndrome: symptoms, causes and treatment.