
Most headaches are tension-type headache or migraine, and few are dangerous. The type is worked out from the story of the pain rather than from a scan, which most people never need. What the pain feels like, where it sits, what comes with it, and what pattern it follows tell you which one it is.
What headaches are
Headache is pain in the head or face. It can be a dull ache or a throbbing pulse, on one side or both, and it usually comes with other symptoms that identify the type.
The pain does not come from the brain, which has no pain receptors. It comes from the blood vessels, muscles, nerves, and coverings around it.
Types of headaches
Headaches fall into two groups. Primary headaches are the condition itself. Secondary headaches signal something else, which is why sorting out the group is the first job of any evaluation.
| Type | Defining pattern | The clue |
|---|---|---|
| Tension-type (primary) | Dull band tightening around the head, mild to moderate, 30 minutes to several days | Tender scalp, neck, and shoulder muscles; stress, poor sleep, or posture |
| Migraine (primary) | Throbbing, often one-sided, hours to days, with nausea and light and sound sensitivity | Worse with activity; may follow visual aura |
| Cluster (primary) | Severe pain around one eye, several attacks a day for weeks, then long free stretches | Watering eye and blocked nostril on the same side, restlessness |
| Exertional (primary) | Pulsing during or after physical effort | Often migraine-related, but a first one needs evaluation |
| Sinus (secondary) | Deep pressure in the forehead, cheeks, and upper teeth | Fever and congestion. Without those, usually migraine |
| Post-traumatic (secondary) | Dull ache after a head injury, days to months | Comes with dizziness and poor concentration |
| Medication-overuse (secondary) | Daily or near-daily, often present on waking | Pain relievers taken on most days for months |
Our migraine guide covers the four phases, aura, and treatment.
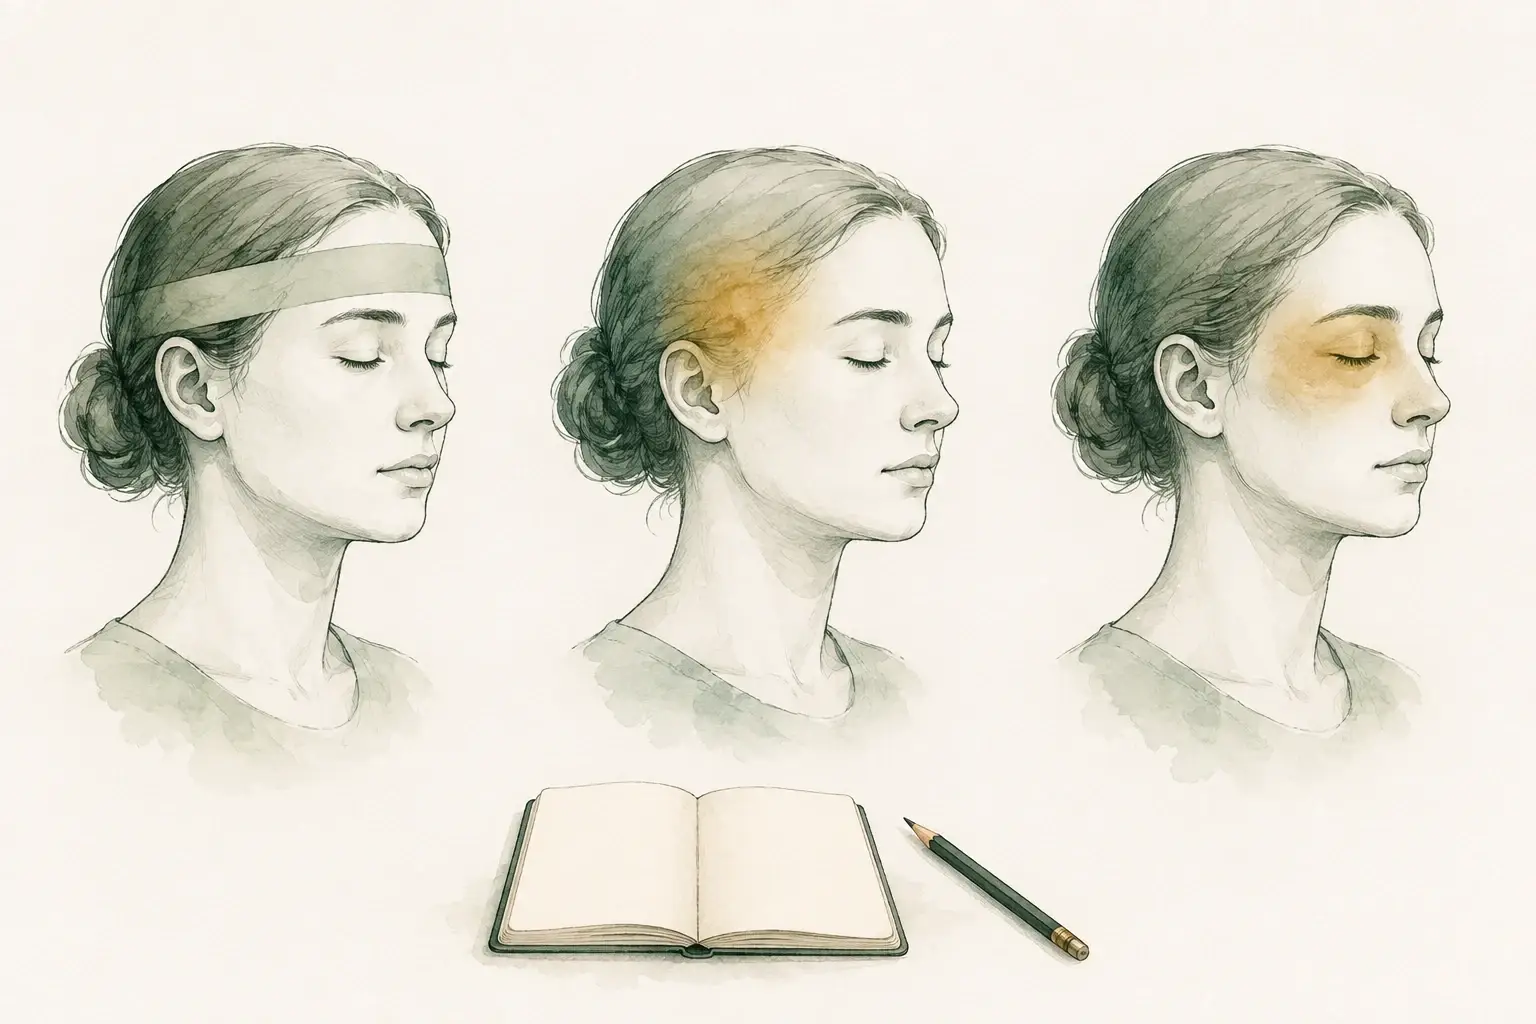
A headache is more than its location
- Pain: How it feels and how long it lasts are useful clues.
- Symptoms: Nausea, light sensitivity, and other changes add context.
- Pattern: A headache history helps guide diagnosis and treatment.
Tension headache vs migraine vs cluster headache
These are the three primary headaches people most often confuse. Side by side, they differ on almost every point.
| Tension-type headache | Migraine | Cluster headache | |
|---|---|---|---|
| Where it hurts | Both sides, like a band around the forehead, temples or back of the head | Often one side, though it can be both, and it can switch sides between attacks | Always one side, in or around one eye or temple |
| How it feels | Pressing or tightening, mild to moderate | Throbbing or pulsing, moderate to severe | Severe, sharp, boring or burning |
| How long | 30 minutes to several days | A few hours to three days | 15 minutes to three hours, up to several times a day, often at the same time of day, for weeks at a time |
| What comes with it | Usually nothing else: no nausea, and at most mild sensitivity to light or to sound | Nausea, sensitivity to light and sound, and in some people an aura first | On the same side: a red, watering eye, a blocked or runny nostril, a drooping eyelid |
| Effect of moving | Not made worse by routine activity | Worse with routine activity, such as climbing stairs | Restlessness: people pace or rock rather than lie still |
| Who tends to get it | Almost anyone; it is the most common headache | More often women, usually starting before 40, often with a family history | More often men, usually starting between 20 and 40 |
| What helps | Over-the-counter pain relievers, sleep, and easing stress and neck strain; a preventive if it becomes frequent | Treating early, a dark quiet room, and a preventive when attacks are frequent | Oxygen through a mask and fast-acting triptans by injection or nasal spray, because tablets act too slowly, plus a preventive through the bout |
Real headaches do not always read like a textbook, and many people have both tension-type headache and migraine. The history and a few weeks of a diary usually settle which is which.
What headache location tells you
Location narrows the type. It rarely identifies a cause by itself, which is why the rest of the pattern matters.
| Location | Most often | Less often | Get it checked the same day if |
|---|---|---|---|
| Top of the head | Tension-type; on its own, rarely a reason for imaging | Migraine | It is worst on waking or lying flat, with nausea or vision change |
| Temples | Tension-type, migraine | Teeth grinding or jaw strain; giant cell arteritis after 50 | You are over 50 and the pain is new (see below) |
| Forehead and behind the eyes | Migraine, tension-type, eye strain | Sinus infection, which comes with fever and congestion; cluster headache behind one eye | It comes with fever and swelling around the eye, or a red, painful eye and blurred vision |
| Back of the head and base of the skull | Neck muscles and joints, tension-type | Occipital neuralgia, which sends brief electric jabs up from the base of the skull | It is new and severe with a stiff neck: that is an emergency, call 911 |
| One side | Migraine, which can switch sides between attacks | Cluster, which stays around the same eye; a headache on exactly the same side every time is worth mentioning | It is new and you are over 50; with weakness, numbness or trouble speaking, call 911 |
| Whole head | Tension-type | Migraine, medication-overuse headache, a headache that comes with fever or illness | It peaked within a minute of starting, or comes with fever, a stiff neck or confusion: call 911 |
Face, cheek or jaw. Brief electric stabs set off by touch, chewing or a breeze point to trigeminal neuralgia, a nerve pain rather than a headache type.
New temple pain after 50. In someone over 50, new temple pain with a tender scalp, a jaw that tires when chewing, or any change in vision needs an urgent same-day medical assessment for inflammation of the temporal arteries, which can threaten sight. Doctors call this giant cell arteritis. Blood tests and a temporal artery biopsy confirm it, but high-dose steroids are started on suspicion, before results, because that is what protects sight. Normal blood tests do not rule it out.
What causes headaches
- Stress and posture: the usual driver of tension-type headache, and the most common cause overall.
- Dehydration and skipped meals: common and easy to fix. Irregular eating is a more reliable trigger than any single food.
- Sleep: too little, too much, or an irregular schedule.
- Environment: strong smells, loud noise, bright light, and in Southern California, Santa Ana winds and wildfire smoke.
- Hormonal changes: estrogen shifts around menstruation, pregnancy, or menopause.
- Overuse of pain relievers, which turns an occasional headache into a daily one.
Identifying your own triggers is the most useful thing you can do without us. A headache diary kept over a few weeks shows a pattern no single visit can: print our one-page headache diary and fill in a line each day, including the days without a headache.
Why you wake up with a headache
A headache that is there when you open your eyes has a shorter list of causes than headache in general, and most of them are fixable.
- Sleep apnea. Interrupted breathing lowers overnight oxygen and produces a dull headache on waking that fades within an hour or two. If you snore, wake unrefreshed, or have been told you stop breathing, a home sleep study is often the most useful test to order.
- Medication-overuse headache. Overnight is the longest gap between doses, so the rebound headache is waiting in the morning.
- Teeth grinding. A tight jaw, worn teeth, or a partner who hears it at night.
- Alcohol, oversleeping, and an irregular schedule. Weekend mornings are the classic time.
- Caffeine withdrawal, if you drink a lot of it during the day.
- Migraine, which often begins in the early morning hours.
One pattern is uncommon and important: a headache that is worst on waking or lying flat, eases when upright, and comes with nausea or visual change can mean raised pressure inside the head, and needs an examination and imaging rather than a stronger painkiller. Relieving a morning headache means finding which of these it is.
Headaches every day or most days
A headache that is there every day, or on most days, wears you down in a way an occasional one does not, and it is the pattern that most needs a neurologist. It usually has one of a few causes, and each is treated differently:
- Medication-overuse headache. Pain relievers taken on too many days start to keep the headache going. The thresholds are in the questions below.
- Chronic migraine. Headache on 15 or more days a month for more than three months, with migraine features on at least eight of them. It often grows out of ordinary migraine as attacks become more frequent.
- Chronic tension-type headache. A band of pressure on 15 or more days a month that has outlasted simple pain relievers, often tied to sleep, stress or neck strain.
- New daily persistent headache. A headache that starts on a day you can remember and does not go away. It needs an evaluation to exclude other causes before it is given that name.
- Sleep apnea. A dull headache on waking most mornings, described above.
What a neurologist does is methodical. A headache diary comes first, so you both see how many headache days you have and on how many of them you take something. If pain relievers are part of the problem, a supervised taper brings them down while a preventive takes over, and the preventive is matched to the headache type and adjusted at follow-up. Our headache neurology service is built around exactly this kind of plan.
Natural remedies for headache relief
Only a few non-drug treatments have held up in trials, and they work alongside medication rather than instead of it: biofeedback and relaxation training, which teach control over muscle tension and the stress response; acupuncture, which has beaten sham treatment; physical therapy when neck pain is part of the picture; regular exercise; and cognitive behavioral therapy for the disability of chronic headache, which we refer out for.
Supplements. The evidence for supplements is specific to migraine, and our migraine page keeps the supplement table with what it shows for each. Tell us what you are taking so we can check for interactions.
One caution on manual therapy. Massage and gentle work on the neck are safe for most people. We advise against high-velocity manipulation of the neck, because of a rare but serious association with injury to the neck arteries that can cause a stroke. Causation is not proven, but the association is enough for us to avoid it.
Medical treatment options
Treatment depends on the type, the frequency, and the disruption.
Over the counter. Ibuprofen or naproxen, acetaminophen, or a combination product with caffeine. These work well for occasional headaches. Taken too often they cause medication-overuse headache, in which the pain relievers themselves keep a daily or near-daily headache going. Reaching for a pain reliever more than two or three days a week is the point to come in and talk.
Prescription. Acute treatments stop an attack: triptans, and the newer gepants. Preventives reduce how often attacks happen: certain antidepressants, anti-seizure medications, blood pressure medications, and the CGRP-targeted antibodies. Prevention is worth discussing once headaches occur more than a few times a month.
Prevention takes patience. Most preventives need several weeks at a steady dose before their effect is clear, so the plan is adjusted over follow-up.

A plan for attacks and prevention
- Attack care: Treatment may aim to relieve an individual headache.
- Prevention: Frequent headaches may call for a preventive approach.
- Review: Medication use and the headache pattern guide adjustments.
When to see a neurologist
Come in if your headaches:
- Are more severe or frequent than they used to be
- Have changed pattern
- Are there on waking most mornings
- Started after a head injury or after age 50
- Cause persistent nausea
- Have stopped responding to over-the-counter medication
The same goes for headaches with a stiff neck, confusion, numbness, weakness, or visual changes.
Go to an emergency department
A sudden, severe headache that peaks within a minute, one with fever and a stiff neck, one with confusion, weakness, trouble speaking, or a seizure, or a severe headache after a head injury needs immediate emergency care, not an appointment. Our article on headache red flags explains each one.
When headaches have started to run your week, it is natural to wonder whether something serious is behind them; most are tension-type or migraine, and few are dangerous. An evaluation at our headache neurology service starts with a 60-minute first visit with Dr. Achillefs Ntranos, MD, in person in Beverly Hills or Los Angeles or by video anywhere in California. It centers on your history and a neurological examination, imaging is ordered only when the story warrants it, and you leave with a written plan. Follow-ups are usually every one to three months and last 30 minutes, and messages between visits are answered within 1 business day. Request a visit; no referral is needed, and the office confirms within 1 business day.
Frequently asked questions
References
- Cleveland Clinic. Headaches: types, causes, symptoms and treatment.
- National Institute of Neurological Disorders and Stroke. Headache.
- Cleveland Clinic. Six reasons why you wake up with headaches.
- International Classification of Headache Disorders, 3rd edition. Medication-overuse headache.
- Biller J, et al. Cervical arterial dissections and association with cervical manipulative therapy: a statement for healthcare professionals from the American Heart Association/American Stroke Association. Stroke, 2014.
- Maz M, et al. 2021 American College of Rheumatology/Vasculitis Foundation guideline for the management of giant cell arteritis and Takayasu arteritis. Arthritis and Rheumatology, 2021.
- Ponte C, et al. 2022 American College of Rheumatology/EULAR classification criteria for giant cell arteritis. Annals of the Rheumatic Diseases, 2022.