These are conditions in which the immune system attacks part of its own nervous system. Because the target varies, so do the symptoms, which is why they are so often recognized late. The field has changed enormously in fifteen years: antibody tests now name conditions that used to be labeled psychiatric illness, unexplained seizures, or idiopathic neuropathy, and most of them respond to treatment.
What are autoimmune neurological diseases?
The immune system normally protects you from infection. In an autoimmune neurological disease it mistakes a protein in the nervous system for a threat and attacks it, with antibodies or with immune cells. Where that protein sits determines everything about the illness: the brain (encephalitis), the spinal cord (myelitis), the optic nerves, the peripheral nerves (neuropathies), or the neuromuscular junction (myasthenia gravis).
Finding the specific antibody matters. It names the disease, points to the treatment, and for some antibodies tells the neurologist to go looking for a tumor.

List of neurological autoimmune diseases
Brain, spinal cord, and optic nerves
| Condition | Hallmark | How treatable |
|---|---|---|
| Demyelinating diseases: multiple sclerosis, NMOSD, MOG antibody disease | Attacks of vision loss, numbness, weakness, or unsteadiness that build over days, with inflammation on MRI | Long-term therapy chosen for the specific diagnosis. Our demyelinating diseases page sets the three side by side |
| Autoimmune encephalitis (NMDA receptor, LGI1, CASPR2) | Memory loss, seizures, and psychiatric change together, over days to weeks | Immunotherapy, and much better the earlier it starts |
| Stiff-person syndrome (anti-GAD) | Painful stiffness and spasms of the trunk and legs | Partly. Immunotherapy plus symptom control |
| Nervous system involvement in lupus, Sjögren's, or sarcoidosis | Seizures, strokes, myelitis, or cranial nerve palsies in someone with, or before, the systemic diagnosis | Treating the systemic disease, with neurology and rheumatology together |
Nerves, neuromuscular junction, and muscle
| Condition | Hallmark | How treatable |
|---|---|---|
| Myasthenia gravis | Weakness that worsens with use and improves with rest. Droopy lids, double vision, trouble swallowing | Several drug classes, including newer targeted therapies |
| Guillain-Barré syndrome | Weakness climbing from the feet over days, often after an infection | Immunoglobulin or plasma exchange. An emergency, since breathing can be affected |
| CIDP | The slower counterpart of Guillain-Barré, relapsing or progressing over months | Responds well, often needing long-term treatment |
| Autoimmune neuropathy with Sjögren's or lupus | Burning feet with normal standard nerve conduction studies | Treat the underlying disease. A skin biopsy confirms small fiber damage |
| Paraneoplastic syndromes | Neurological symptoms that appear before the cancer causing them is found | Treating the tumor is part of treating the syndrome |
| Autoimmune myositis | Weakness of the shoulders and hips over weeks to months, sometimes with a rash | Immunosuppression, with muscle enzymes and antibodies guiding the choice |
The rarer entries, such as Lambert-Eaton myasthenic syndrome, autoimmune autonomic ganglionopathy, Susac syndrome, and steroid-responsive encephalopathy with thyroid antibodies, are found the same way: by matching the pattern of symptoms to an antibody. Antibody testing is what separates these conditions from one another, and it is also what has expanded the list. Several of them were not diagnosable at all twenty years ago.
Visual guide
Where immune conditions can act
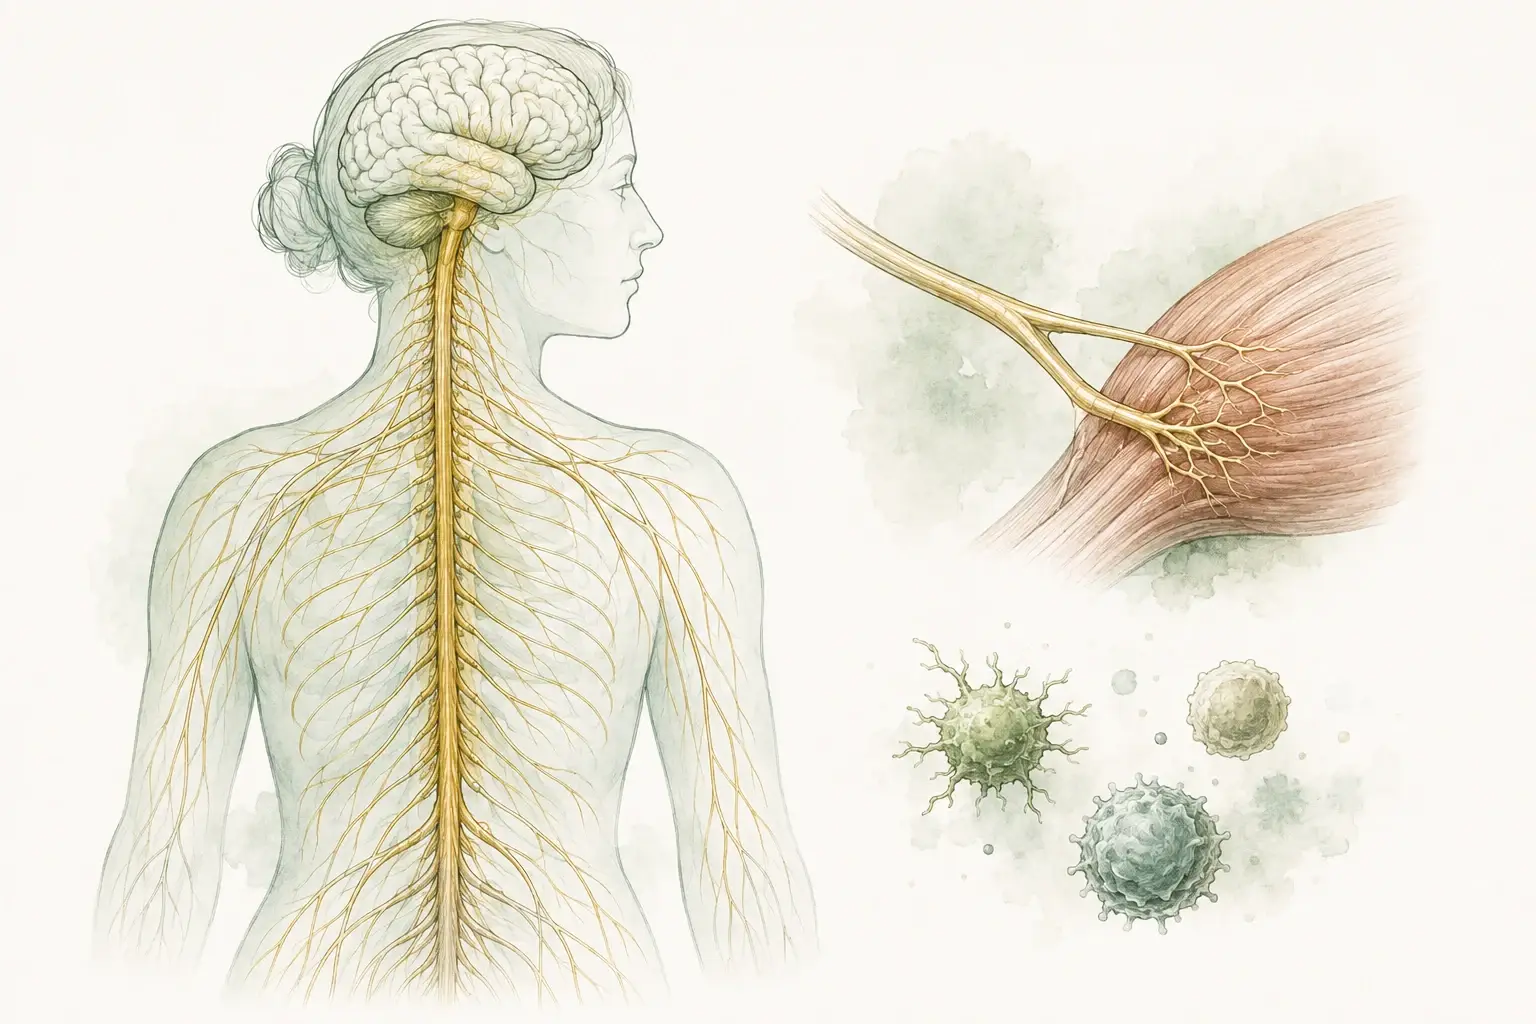
- Central nerves: Some conditions involve the brain or spinal cord.
- Peripheral nerves: Others affect nerves outside the brain and spinal cord.
- Nerve and muscle: Certain conditions affect communication between nerves and muscles.
Symptoms and warning signs
Symptoms follow the target rather than the diagnosis:
- Brain. New confusion, memory loss, seizures, hallucinations, or a change in personality or behavior, often arriving together.
- Spinal cord and optic nerves. Vision loss in one or both eyes, a band of numbness around the trunk, weakness below a level, bladder changes.
- Peripheral nerves. Numbness, burning, or shooting pain, weakness with lost reflexes, or unsteadiness from not feeling the feet.
- Neuromuscular junction and muscle. Weakness that gets worse the longer a muscle is used: drooping eyelids by evening, double vision, trouble chewing or swallowing, or difficulty rising from a chair.
Do not wait for an appointment
Rapidly worsening weakness, trouble swallowing or breathing, new confusion with seizures, or weakness climbing from the feet up the body can all be autoimmune emergencies. Go to an emergency department. We are glad to take over the care afterwards.
How they are diagnosed
The workup follows the part of the nervous system involved, so the first job is localizing the problem to brain, cord, nerve, or muscle.
| Test | What it answers |
|---|---|
| History and examination | Where the problem is, and how fast it arrived. Recent infections and cancer history matter here |
| Antibody blood tests | Which specific condition, and whether a tumor search is needed |
| MRI of brain or spinal cord | Inflammation, demyelination, or a structural cause instead |
| Lumbar puncture | Inflammatory cells and antibodies produced inside the nervous system |
| Nerve conduction studies and EMG | Whether the problem is in the nerve, the muscle, or the junction between them |
A negative antibody panel does not close the question. Antibody-negative forms of most of these conditions exist and are diagnosed on the clinical picture, the MRI, and the spinal fluid.
Visual guide
Putting the evidence together
- Examination: The history and neurological findings guide the workup.
- Testing: MRI, blood tests, spinal fluid, or nerve studies may be selected.
- Interpretation: Results are considered together to identify the condition.
Treatment
Treatment has two aims: calm the immune attack, and manage what it has already caused.
Calming the attack usually starts with corticosteroids, immunoglobulin, or plasma exchange, then moves to rituximab or another longer-acting agent to prevent relapse. Where a tumor is driving the process, removing it is part of the treatment.
Managing what is left means anti-seizure medication, neuropathic pain treatment, and physical, occupational, or speech therapy, depending on what the illness affected.
Newer targeted therapies that block the FcRn receptor or the complement system are now approved for myasthenia gravis and NMOSD, and cell-based therapies are in trials for several antibody-mediated conditions. If a trial fits your situation, we will say so and help you find it.
When to see a neurologist
See one for new weakness, numbness, vision changes, unsteadiness, seizures, or a change in memory, thinking, or behavior that develops over days to weeks, especially if it fluctuates or keeps progressing. If a nerve or muscle problem has been called idiopathic and it is still getting worse, an autoimmune cause is worth revisiting.
An autoimmune neurology evaluation here is a 60-minute visit with Dr. Ntranos, whose training and research were in neuroimmunology, at Mount Sinai and then Johns Hopkins. He reviews your prior records and imaging himself and orders the antibody panels, MRI, spinal fluid, and nerve studies the picture calls for, all through your insurance. Nerve conduction studies and EMG are done at an outside laboratory, and infusions at an infusion center. We arrange both and handle the prior authorizations. If you have a diagnosis that does not seem to fit, we also offer second opinions. You can request a visit in Beverly Hills or West Los Angeles, or by video anywhere in California.
Frequently asked questions
References
- Multiple Sclerosis International Federation. Atlas of MS, 3rd edition, 2020.
- Graus F, et al. A clinical approach to diagnosis of autoimmune encephalitis. The Lancet Neurology, 2016.
- National Institute of Neurological Disorders and Stroke. Myasthenia gravis.
- Cleveland Clinic. Neuroimmunology: what it is and disorders.