Symptoms that came on over days to weeks with no clear cause, or an antibody result nobody has explained, can leave you without a name for what is happening. Autoimmune neurology is care for conditions in which the immune system attacks the brain, spinal cord, optic nerves or peripheral nerves, and it starts with a 60-minute visit that ends with a working diagnosis and a testing plan. Many of these conditions were described only in the last twenty years, are often mistaken for psychiatric illness, epilepsy, or dementia, and are treatable when recognized.
Dr. Achillefs Ntranos, MD trained in this area: a fellowship in multiple sclerosis and demyelinating diseases at Mount Sinai, postdoctoral neuroimmunology research at Johns Hopkins, then Assistant Professor of Neurology at Mount Sinai before founding the clinic in 2022.
What autoimmune neurology is
Antibodies or immune cells target one specific protein in the nervous system, and which protein is attacked determines the illness. Antibodies against a receptor on brain cells cause encephalitis. Antibodies against two proteins, aquaporin-4 and MOG, inflame the optic nerves and spinal cord, causing neuromyelitis optica spectrum disorder (NMOSD) and MOG antibody disease (MOGAD). Antibodies against peripheral nerves cause weakness and numbness that passes for an ordinary neuropathy.
A neuroimmunologist, also called an autoimmune neurologist, is a neurologist with additional training in these conditions. People searching for a brain inflammation doctor, an encephalitis specialist, or a doctor who treats transverse myelitis, NMO (once called Devic's disease) or MOG antibody disease usually mean this. These conditions are distinct from multiple sclerosis, and telling them apart matters because some MS treatments make them worse.
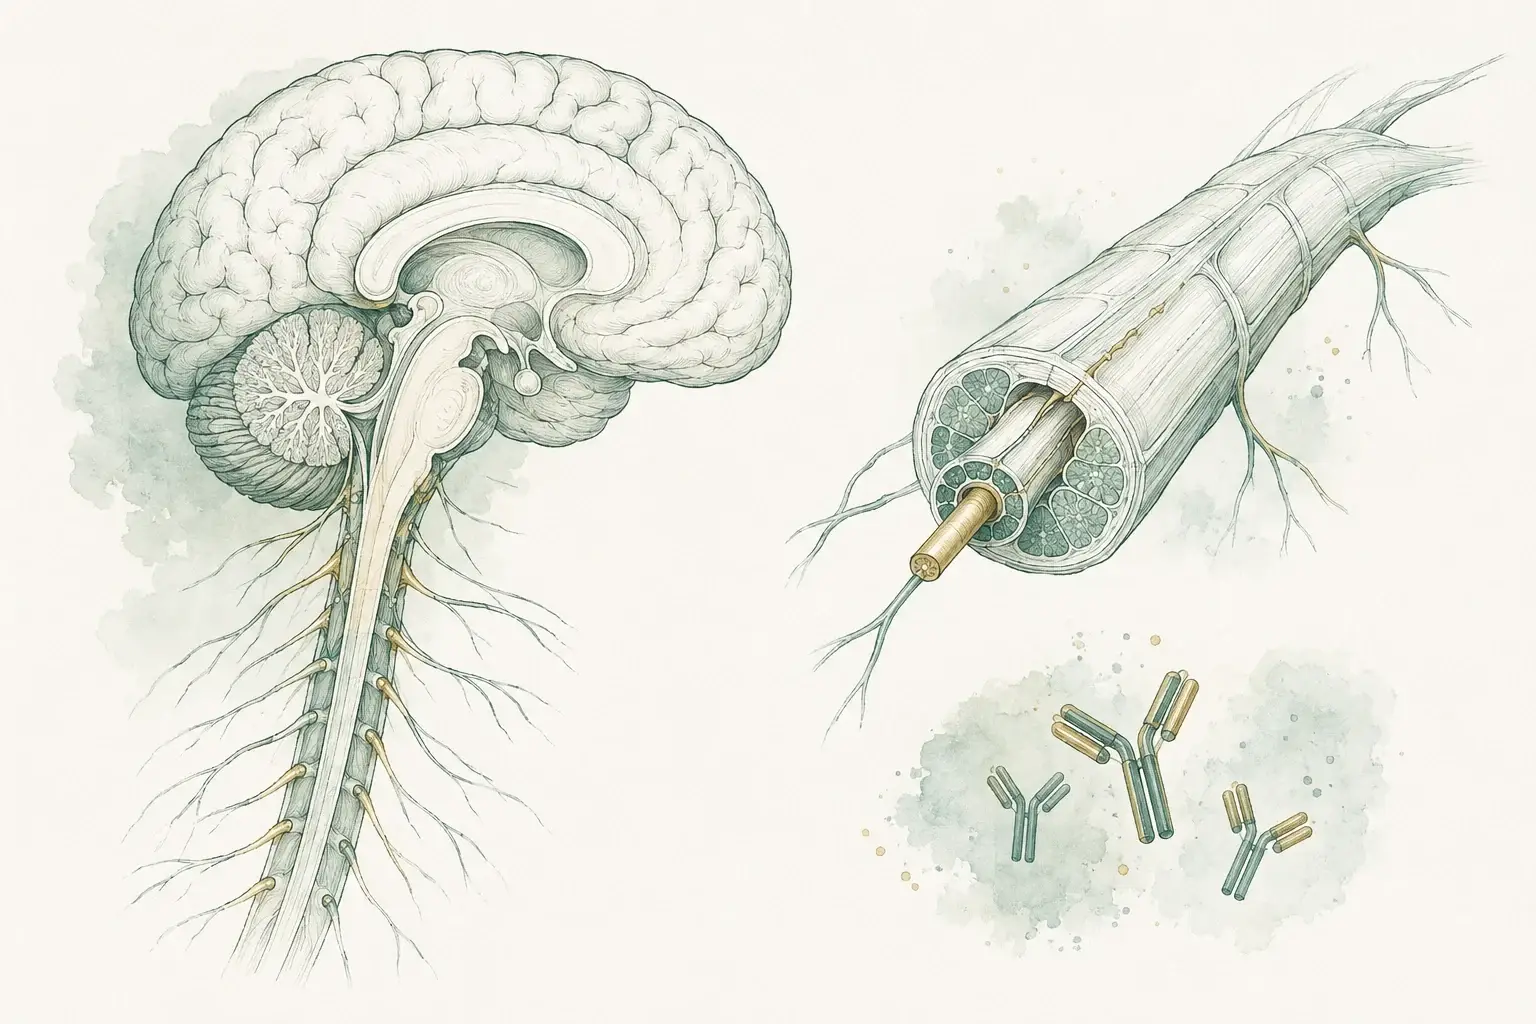
Where immune inflammation can occur
- Brain: inflammation can affect memory, thinking or seizures.
- Optic nerves and spinal cord: inflammation can affect vision, strength or sensation.
- Peripheral nerves: immune injury can cause weakness and numbness.
Conditions we evaluate and treat
| Condition | What usually points to it |
|---|---|
| Autoimmune encephalitis: NMDA receptor, LGI1, CASPR2 | Confusion, memory loss, new seizures, or psychiatric symptoms over days to weeks |
| NMOSD (formerly Devic's disease) and MOGAD | Optic nerve and spinal cord inflammation, with aquaporin-4 or MOG antibodies |
| Transverse myelitis | Numbness, weakness, or bladder change below a level on the spinal cord |
| Autoimmune epilepsy | New seizures resistant to standard medication, often with memory change |
| Stiff person syndrome, autoimmune movement disorders | Progressive stiffness and spasms, or new chorea or tremor with no structural cause |
| Guillain-Barré syndrome and CIDP | Weakness and numbness with lost reflexes, over days in GBS and months in CIDP |
| Paraneoplastic syndromes | An immune response to a cancer, sometimes one not yet found, attacking nerves |
We also see neuroinflammation and nervous system involvement in lupus, Sjögren's, and sarcoidosis. Our autoimmune conditions page goes deeper on each.
Autoimmune encephalitis
In its acute phase this is a hospital condition, and the right place is an emergency department, not an outpatient appointment.
An outpatient neuroimmunologist fits before and after that phase: when symptoms are subacute and the question is whether an autoimmune cause is worth pursuing, when someone is discharged and needs immunotherapy managed, and when a label of dementia or epilepsy does not fit. Our article on autoimmune encephalitis symptoms and diagnosis explains why the speed of onset is the clue and why the diagnosis does not wait for antibody results.
How the evaluation works
The history covers how symptoms began and evolved, infections or vaccinations in the weeks before onset, autoimmune disease in you or your family, cancer history, and what has already been tried. The neurological examination looks for signs that separate an inflammatory process from a degenerative or structural one.
From there we order what the working diagnosis requires: MRI with contrast; spinal fluid by lumbar puncture, arranged at a facility that performs it under fluoroscopy; EEG for suspected seizures; neuropsychological testing for cognitive involvement; a small fiber skin biopsy, performed in our Beverly Hills office; and cancer screening when a paraneoplastic syndrome is possible.
Antibody panels are where the laboratory matters as much as the order. We send them to the reference laboratories that developed and validated the assays, not wherever a local draw station routes them.
Two cautions. A negative panel does not exclude an autoimmune cause: antibody-negative cases exist and are diagnosed on the clinical picture, MRI, and spinal fluid. And a low-level positive in someone whose story does not fit is more often a false positive than a diagnosis. A positive antibody on its own does not make a diagnosis. The clinical picture, the MRI, and the spinal fluid have to fit it too.
Immune dysfunction testing: what we test, and what we do not
The phrase covers two different things. In neurology it means looking for an immune system that is attacking the nervous system: neural antibody panels in blood and spinal fluid, spinal fluid cell counts and oligoclonal bands, MRI with contrast, and where relevant EEG or nerve studies. That is what we do.
It does not mean testing for immunodeficiency, a weakened immune system that causes repeated infections, or for allergy. Those belong to an allergist-immunologist, and we will point you to one if that is the real question. It also does not mean the broad "immune panels" sold by wellness clinics, which rarely change a neurological diagnosis. If you bring one, we are glad to read it in context.
What to expect, visit by visit
First visit, 60 minutes
History, examination, a working diagnosis, and orders for the testing that will test it. Send records ahead through patient tools.
Testing, usually a few weeks
Blood draws can be done locally. MRI, EEG, and lumbar puncture are scheduled in the same window, and we handle the prior authorizations.
Results visit, 30 minutes
In person or by video. What the results show, what they do not, the diagnosis or the next step, and the plan in writing.
Treatment and monitoring
Prescriptions, infusion scheduling, and the laboratory monitoring immunotherapy requires. You can message Dr. Ntranos between visits through the patient portal, and messages are answered within 1 business day.
If your symptoms need hospital care, we will tell you to go to an emergency department, and we can manage your treatment after discharge.

Reading autoimmune results in context
- Clinical picture: how symptoms began and evolved guides interpretation.
- Supporting evidence: MRI and spinal fluid may support or challenge a diagnosis.
- Test limits: a positive antibody alone is insufficient, and a negative panel does not exclude every case.
Treatment
- Acute immunotherapy to stop the attack: high-dose corticosteroids, or infusion treatments that supply or remove antibodies. We prescribe and handle prior authorization. Infusions are given at an infusion center, not in our office.
- Long-term immunotherapy to prevent relapse: an oral immunosuppressant or an infused antibody therapy, including the newer agents approved for specific conditions such as NMOSD and myasthenia gravis, monitored with regular blood work. The choice follows the diagnosis, and the condition pages go into the options.
- Symptomatic treatment for seizures, spasticity, pain, sleep, and mood, rehabilitation by referral, and treatment of the underlying cancer with oncology in paraneoplastic syndromes. Where a clinical trial fits, we will say so.
Long-term follow-up
Most of these conditions need years of follow-up, which is where relapses are caught early and side effects are managed: 30-minute visits at an interval set by your condition, laboratory monitoring for immunosuppressant safety, repeat MRI when indicated, and forms for work and disability. Part of it is deciding, carefully, when treatment can be reduced.
When to seek an evaluation
Consider one if neurological symptoms came on over days to weeks with no clear cause, if new seizures came with memory or psychiatric change, if memory loss moved faster than a dementia would, if symptoms appeared alongside a known autoimmune disease or a cancer diagnosis, or if a positive neural antibody was left unexplained.
When not to wait for an appointment
Rapidly worsening confusion, a first seizure, sudden vision loss, or new weakness spreading over hours need emergency evaluation. Call 911 or go to the nearest emergency department. We are glad to take over afterwards.
When a label of dementia, epilepsy or psychiatric illness has never quite fit, the first visit goes back to how your symptoms began and changed. It is 60 minutes with Dr. Ntranos, in person in Beverly Hills or Los Angeles, or by video anywhere in California, and new patients are usually seen the same or next business day. Dr. Ntranos has 200+ five-star reviews on Google and Zocdoc. Follow-ups are usually every one to three months and last 30 minutes. Request a visit with no referral, and the office confirms your request within 1 business day. Visits are one flat fee with no facility charges, you receive a superbill, and most PPO plans reimburse 50–80%, depending on out-of-network benefits and deductible. See our billing page.
Frequently asked questions
References
- Graus F, et al. A clinical approach to diagnosis of autoimmune encephalitis. The Lancet Neurology, 2016.
- Cleveland Clinic. Neuroimmunology: what it is and disorders.
- National Institute of Neurological Disorders and Stroke. Transverse myelitis.
- Bien CG. Overinterpretation and overtreatment of low-titer antibodies against contactin-associated protein-2. Frontiers in Immunology, 2018;9:703.