
Most people suspected of obstructive sleep apnea no longer need a night in a laboratory. If someone has heard you stop breathing at night, our test records your breathing, oxygen and brain waves over three nights in your own bed. A board-certified sleep medicine physician reads it, and Dr. Ntranos goes through the result and a plan with you.
Home sleep apnea testing in Los Angeles: how ours works
A home sleep apnea test is a portable recording of your breathing, oxygen, heart rate, and position while you sleep. It is the standard way to diagnose obstructive sleep apnea in adults with typical symptoms.
Dr. Achillefs Ntranos, MD orders the study after a consultation, in person in Beverly Hills or West Los Angeles or by video anywhere in California. A board-certified sleep medicine physician scores and interprets the recording. Dr. Ntranos then reads that report alongside your history and examination and goes through the result and the plan with you.
We come at apnea from the neurology side. Patients arrive with morning headaches, brain fog, memory complaints, or fatigue, and untreated apnea is part of the cause more often than people expect.
| What the device records | Why it matters |
|---|---|
| Airflow and breathing effort | Finds pauses and partial obstructions, and separates obstructive from central events |
| Blood oxygen | Records the drops that follow each event |
| Heart rate | Rises with each arousal |
| Body position | Shows whether apnea is worse on your back, which changes the treatment |
| EEG | Defines sleep, wake, and sleep stage |
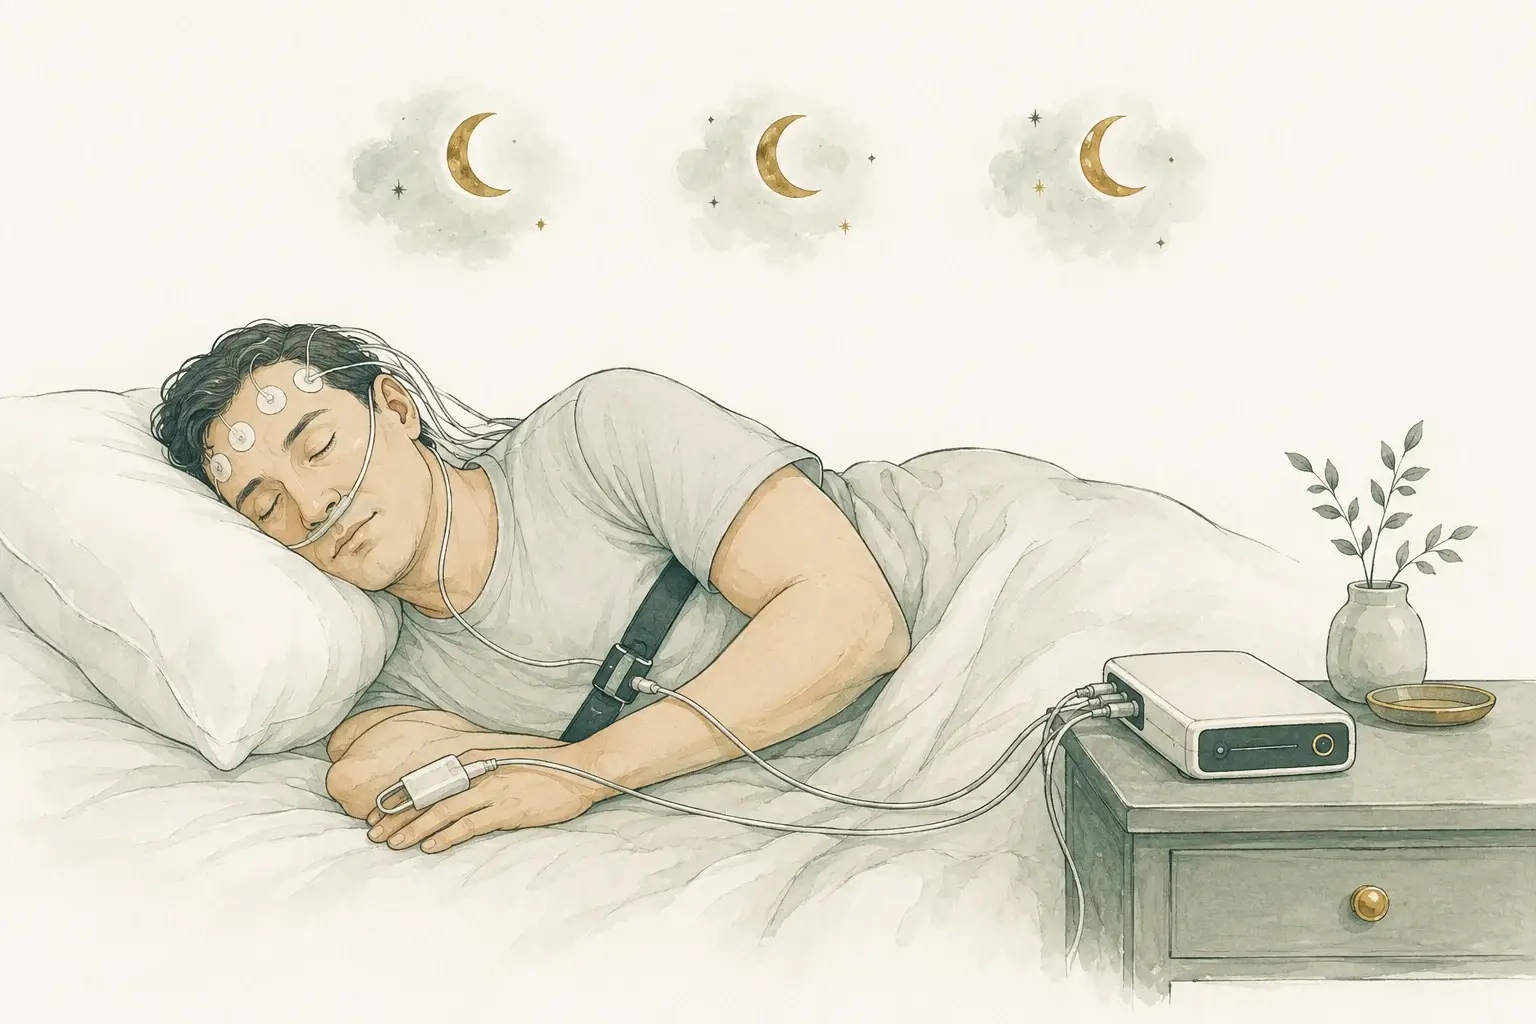
What a home sleep recording captures
- Breathing: airflow and effort show pauses and partial obstructions.
- Body signals: oxygen, heart rate and position add context.
- Brain waves: EEG helps distinguish sleep from wake and identify sleep stages.
Why the EEG channels matter
The main measure of sleep apnea is the apnea-hypopnea index: breathing events per hour of sleep. The denominator is hours of sleep, not hours in bed.
Most home devices do not record brain waves, so they have to guess when you were asleep from movement and breathing. Lying still and awake at 3 a.m. gets counted as sleep, so estimated sleep time runs long and the index runs low, and mild to moderate apnea can slip under the threshold and be called normal.
Our device is a type 3 home recorder with EEG channels that can distinguish sleep stages. It is not the full electrode montage of a laboratory study, but it tells sleep from wake and identifies REM, so the index is calculated against true sleep time. That is the difference between a genuine apnea-hypopnea index and the respiratory event index a device without EEG can only calculate against recording time. It also shows whether events cluster in REM sleep, which is common and invisible when REM is never identified.
Recording time is one of several reasons home tests can underestimate severity. They also miss hypopneas that end in an arousal rather than an oxygen drop, and a sensor that comes loose during the night costs data a technologist would have replaced in a laboratory. Recording three nights limits the damage a bad sensor night does, and the EEG channels let the scorer see the arousals a device without brain waves would miss.
Three nights, read by a sleep specialist
- Three nights, not one. Apnea severity differs between a night on your back after a glass of wine and a night on your side, and one poor recording leaves a single-night test inconclusive.
- Read by a specialist, not an algorithm. A board-certified sleep medicine physician reviews the recording rather than signing off an automated summary.
- One to two weeks from consultation to results visit, in most cases.
What to expect, step by step
The consultation
A visit with Dr. Ntranos, in person or by video anywhere in California. Snoring, witnessed pauses, waking unrefreshed, morning headaches, and hard-to-control blood pressure are the symptoms that warrant testing. He takes the history, examines you, and decides whether a home test is right or you need an in-lab one.
The device arrives
A small recorder with instructions for the nasal cannula, chest belt, oxygen sensor, and EEG electrodes. Setup takes a few minutes each night.
Three nights at home
Sleep as you normally do, on your usual schedule, with no extra naps and no unusual amount of alcohol. The device records silently.
Send it back
Return the device by mail using the instructions that come with it.
Scoring and results
A board-certified sleep medicine physician scores the apneas, oxygen drops, arousals, sleep stages, and position, and interprets the study. Dr. Ntranos reviews that report and sees you, usually within one to two weeks. You get the index, the severity, and a written plan.
When a home test is the wrong test
A home study is built for uncomplicated adults whose symptoms indicate an increased risk of moderate to severe obstructive sleep apnea. It is the wrong test if central apnea is suspected, meaning pauses because the brain does not send the signal to breathe. It is also wrong with significant heart or lung disease, weak breathing muscles, known or suspected hypoventilation (shallow breathing that lets carbon dioxide build up), regular opioid use, or a prior stroke. A suspected second sleep disorder, such as narcolepsy, REM behavior disorder, severe insomnia or seizures during sleep, also rules it out. If a home test comes back negative, inconclusive, or technically inadequate, the next step is an in-lab study. A negative home test does not rule out sleep apnea. We refer you to an accredited sleep laboratory and follow the result.

From recording to a plan
- Return: mail the device back using the supplied instructions.
- Review: a sleep medicine physician scores and interprets the study.
- Next step: Dr. Ntranos explains the plan; a negative or inadequate home test may need an in-lab study.
Treatment after the diagnosis
- CPAP is the most effective treatment for moderate and severe apnea. We write the prescription and coordinate with a supplier who fits the mask. Modern machines report usage and residual events, which we review later.
- An oral appliance, a custom mandibular advancement device made by a sleep dentist, suits mild to moderate apnea or people who cannot tolerate CPAP.
- Position and weight. Side-sleeping when the apnea is mainly on your back, and weight management where it applies. Our article on lifestyle and neurological health covers this.
- Follow-up. Treatment is only as good as its use, so we check in after it starts, by video where easier.
We do not perform sleep apnea surgery or hypoglossal nerve stimulation. When those are worth considering, we say so and refer you to an ENT surgeon.
Once the apnea is treated we revisit the symptoms that brought you in. Headaches, fog, and memory complaints often improve. When they do not, a neurological evaluation looks further.
Cost, and how to request a visit
Our visits are flat-fee and not billed to insurance. You receive a superbill, and most PPO plans reimburse 50–80%, depending on out-of-network benefits and deductible. HSA and FSA cards are accepted. Our office confirms how the study itself is billed before the device is sent. See our billing page.
If you snore, wake unrefreshed, or push through morning headaches or daytime fog nobody has explained, request a visit or call (310) 774-7025. A first visit with Dr. Ntranos is 60 minutes, in person in Beverly Hills or Los Angeles, or by video anywhere in California. If a home test suits you, results and a written plan usually follow in one to two weeks. Follow-ups are usually every one to three months and last 30 minutes. No referral is needed; the office confirms your request within 1 business day.